




End-stage renal disease and hemodialysis impose substantial physical and emotional demands that compromise patients’ psychological well-being. Psychological resilience – the capacity to adapt positively to chronic adversity – plays a protective role, yet its sociodemographic and gender-related determinants remain poorly characterized in hemodialysis populations.
ObjectiveTo evaluate psychological resilience in adults receiving maintenance hemodialysis and to examine its association with gender, educational level, and clinical variables.
MethodsA cross-sectional study was conducted in 55 hemodialysis patients at the Gómez Ulla Central Defense Hospital (Madrid, Spain). Sociodemographic and clinical data were collected, and resilience was assessed using the 14-item Resilience Scale (RS-14). Statistical analyses included independent-samples t-tests, Spearman's correlations, and multiple linear regression.
ResultsPatients reported moderate resilience levels (mean=74.02, SD=13.99). Men showed significantly higher resilience than women (77.74 vs. 67.50; p=0.008). Educational attainment correlated positively with resilience (ρ=0.307; p=0.023). In the multivariate model, gender and education together explained 22% of the variance in resilience scores (R2=0.22), while clinical variables showed no significant associations.
ConclusionsThis preliminary study suggests that gender and educational level may influence psychological resilience in patients undergoing hemodialysis. These associations should be interpreted with caution due to the small, single-center sample and the absence of key psychosocial and contextual variables. Larger, adequately powered multicenter studies incorporating multidimensional gender measures and broader sociodemographic indicators are needed to clarify the mechanisms shaping resilience in ESRD. Tailored psychosocial interventions may help strengthen emotional adaptation in vulnerable groups.
La enfermedad renal terminal y la hemodiálisis imponen importantes demandas físicas y emocionales que comprometen el bienestar psicológico del paciente. La resiliencia psicológica – capacidad de adaptación positiva ante la adversidad crónica – desempeña un papel protector; sin embargo, sus determinantes sociodemográficos y relacionados con el género están escasamente caracterizados en poblaciones en hemodiálisis.
ObjetivoEvaluar la resiliencia psicológica en adultos sometidos a hemodiálisis de mantenimiento y examinar su asociación con el género, el nivel educativo y variables clínicas.
MétodosSe realizó un estudio transversal en 55 pacientes en hemodiálisis en el Hospital Central de La Defensa Gómez Ulla (Madrid, España). Se recogieron datos sociodemográficos y clínicos, y la resiliencia se evaluó mediante la Escala de Resiliencia de 14 ítems (RS-14). Los análisis estadísticos incluyeron t de Student para muestras independientes, correlaciones de Spearman y regresión lineal múltiple.
ResultadosLos pacientes presentaron niveles moderados de resiliencia (media=74,02; DE=13,99). Los hombres mostraron resiliencia significativamente mayor que las mujeres (77,74 vs. 67,50; p=0,008). El nivel educativo correlacionó positivamente con la resiliencia (ρ=0,307; p=0,023). En el modelo multivariante, el género y la educación explicaron conjuntamente el 22% de la varianza en las puntuaciones de resiliencia (R2=0,22), mientras que las variables clínicas no mostraron asociaciones significativas.
ConclusionesEste estudio preliminar sugiere que el género y el nivel educativo pueden influir en la resiliencia psicológica en pacientes sometidos a hemodiálisis. Estas asociaciones deben interpretarse con cautela debido al reducido tamaño muestral, el carácter monocéntrico del estudio y la ausencia de variables psicosociales y contextuales clave. Se requieren estudios multicéntricos más amplios, con potencia estadística suficiente e incorporación de medidas multidimensionales de género y de indicadores sociodemográficos más amplios, para clarificar los mecanismos que modulan la resiliencia en la enfermedad renal terminal. Intervenciones psicosociales específicas podrían contribuir a fortalecer la adaptación emocional en los grupos más vulnerables.
End-stage renal disease (ESRD) represents a major global health burden due to its profound physical, emotional, and psychosocial consequences. Hemodialysis (HD), the most widely used renal replacement therapy, imposes sustained lifestyle restrictions, treatment fatigue, and symptom burden that negatively affect psychological well-being and quality of life in affected patients.1 In this context, psychological resilience – defined as the capacity to adapt positively to chronic adversity – has emerged as a key protective factor facilitating emotional adjustment and treatment adherence.2
From a biological perspective, resilience is supported by adaptive neuroendocrine and neurotrophic mechanisms. These include efficient regulation of the hypothalamic–pituitary–adrenal axis, faster cortisol recovery following stress, and increased expression of brain-derived neurotrophic factor, which promotes synaptic plasticity and emotional regulation.3 In chronic disease populations, higher resilience levels have consistently been associated with lower psychological distress and improved quality of life.4
Although resilience has been widely studied in conditions such as cancer, cardiovascular disease, and diabetes, its role in HD populations remains insufficiently explored. Available evidence suggests that resilience may mediate the relationship between disease-related distress and psychological outcomes, reinforcing its relevance as a modifiable psychosocial resource in chronic illness. However, studies specifically addressing resilience in HD patients – and its sociodemographic and clinical determinants – are scarce.5
Gender represents a particularly relevant yet underexplored dimension in nephrology research. Unlike biological sex, which refers to chromosomal and anatomical characteristics, gender is a multidimensional sociocultural construct encompassing identity, social roles, norms, power relations, and lived experiences.6 Gender shapes exposure to stressors, access to resources, coping behaviors, and emotional responses, influencing psychological adaptation beyond biological differences alone.7
In chronic illness contexts, gender-related factors such as caregiving responsibilities, employment demands, economic autonomy, social support networks, and experiences of stigma or discrimination have been shown to influence resilience and coping strategies.7–9 In HD populations, women often assume a disproportionate burden of unpaid caregiving and domestic responsibilities, which may increase emotional strain and limit restorative coping resources.9 Conversely, men tend to rely more on instrumental coping strategies and report different patterns of social support, shaping distinct resilience pathways.8,9
Beyond gender, several sociodemographic and clinical factors may also influence resilience in HD. Educational level, as a determinant of health literacy, has been associated with improved illness understanding, problem-solving capacity, and adaptive coping strategies.10 Marital status and relational context may shape emotional adjustment through perceived support and shared coping.11 Clinical characteristics – such as vascular access type, comorbidity burden, and time on renal replacement therapy – reflect treatment complexity and symptom burden and may affect psychological well-being and resilience profiles.12–14
Although resilience has been examined in patients undergoing HD and kidney transplantation,15 few studies have focused specifically on the stressors inherent to HD, including invasive vascular access, dietary and fluid restrictions, infection risk, fatigue, and long-term treatment burden.16–19 These HD-specific demands warrant targeted investigation.
Given the limited evidence on resilience among HD patients – particularly with respect to gender differences and sociodemographic and clinical correlates – further research is needed. The present study aims to assess psychological resilience in patients undergoing maintenance HD, with a specific focus on gender differences and the influence of sociodemographic and clinical variables. We hypothesize that resilience levels differ by gender and are modulated by factors such as educational attainment, comorbidity burden, treatment duration, and vascular access type.
Materials and methodsStudy design and settingThis quantitative, cross-sectional observational study was conducted from March to December 2024 at the Hemodialysis Unit of Central Defense Hospital ‘Gómez Ulla’ in Madrid, Spain. This 200-bed public tertiary care hospital serves both civilian and military populations and includes a dedicated HD unit with 20 stations and approximately 70 patients weekly.
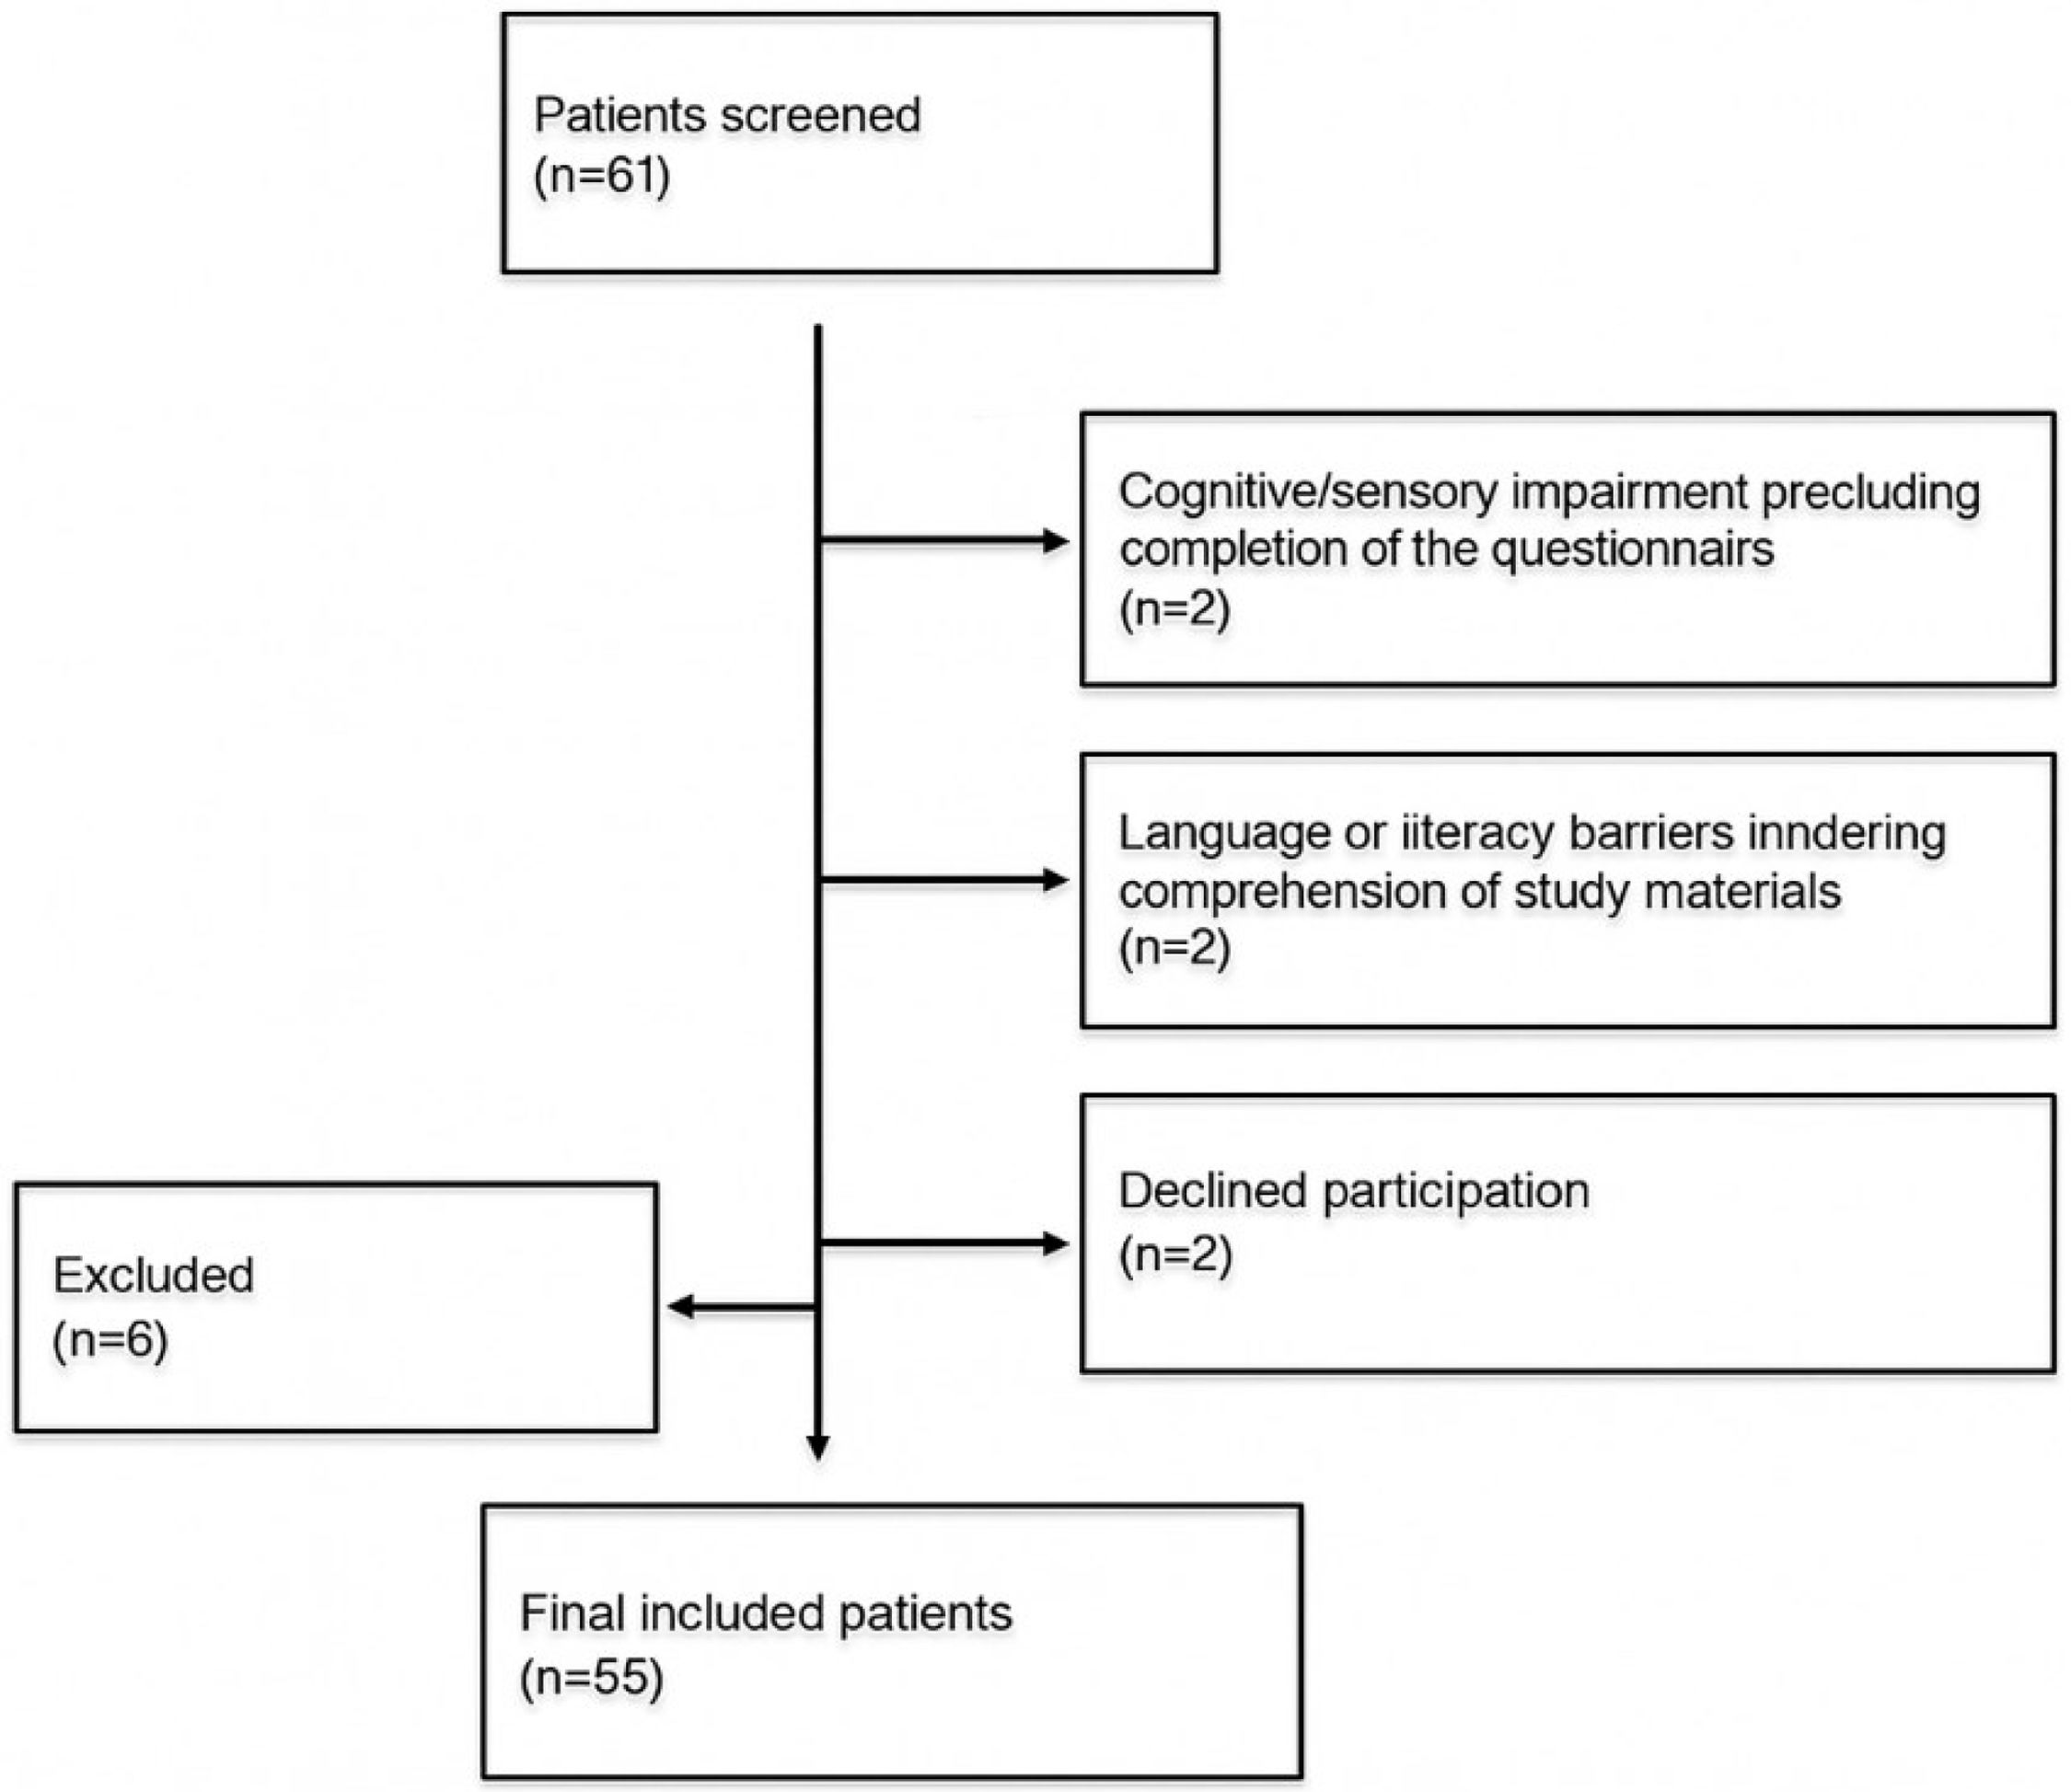
Selection criteriaParticipants were recruited through consecutive nonprobabilistic sampling from the hemodialysis unit. A total of 61 patients were screened, and 55 were included, as detailed in Fig. 1. Six individuals were excluded during screening: two due to cognitive or sensory limitations preventing reliable questionnaire completion, two because of language or literacy barriers, and two who declined participation.

Eligible participants were adults (≥18 years) diagnosed with end-stage renal disease, receiving maintenance hemodialysis for at least 12 months, able to read Spanish, and capable of independently completing a self-administered questionnaire. Written informed consent was obtained before enrollment. Patients undergoing interfacility transfer, recent kidney transplantation, acute hospitalization, or any condition compromising the validity of questionnaire responses were not considered for inclusion (Fig. 1).
This study was designed and reported following the STROBE guidelines. A fully adapted checklist indicating the precise location of each item within the final paginated manuscript is provided in Supplementary Table S1.
Sample-size determinationThe sample size was estimated for a national HD population of 7084 patients (Spanish Renal Patient Registry, 2021) using a 95% confidence level, 5% margin of error, and conservative prevalence (p=0.5). The initial estimate was 384 participants; applying a finite-population correction reduced this to 364.45. Calculations were performed with EPIDAT 4.2. The final sample of 55 patients falls short of this threshold, limiting statistical power and generalizability.
Participant selection and representativenessAlthough randomization was not feasible due to staffing and care continuity constraints, sample characteristics were compared with national registry data. The cohort's mean age (67.7 years) and gender distribution (63.6% men) were consistent with national trends, supporting representativeness and external validity.
Data collection procedurePatients were approached during HD sessions. After verifying eligibility, they received detailed study information and provided written consent. A self-administered questionnaire was completed during dialysis under the investigator's supervision.
Measurement instrumentsPsychological resilience was assessed using the linguistically and culturally validated Spanish version of the 14-item Resilience Scale (RS-14).20,21
The RS-14 evaluates five core dimensions: perseverance, self-reliance, equanimity, meaningfulness, and existential aloneness. Items are scored on a 7-point Likert scale (1=strongly disagree to 7=strongly agree), yielding total scores from 14 to 98. Resilience levels were categorized as follows: very low (14–56), low (57–64), moderately low (65–73), moderate (74–81), moderately high (82–90), and high (91–98), enabling nuanced interpretation of coping capacity and psychological adaptability.
Clinical and sociodemographic variablesClinical, sociodemographic, and psychosocial data were obtained from two sources: the electronic medical record (clinical variables extracted by trained personnel following a standardized protocol) and a self-administered questionnaire completed during the HD session (sociodemographic variables and resilience assessed using the validated Spanish RS-14).
Statistical analysisData were analyzed using IBM SPSS Statistics version 30. Descriptive statistics (means, standard deviations, frequencies, and percentages) were used to summarize sociodemographic and clinical variables. Normality of continuous variables was evaluated with the Shapiro–Wilk test.
Group comparisons were performed using independent samples t-tests (gender-based differences in resilience) and one-way ANOVA for variables with more than two categories (education level, dialysis duration). Post hoc tests with Bonferroni correction were applied as appropriate. Spearman's rho was used to assess correlations between resilience scores and continuous variables (age, time on dialysis).
A multiple linear regression model was constructed to identify sociodemographic and clinical predictors of resilience. Predictor independence was verified through variance inflation factors (VIFs), with thresholds <5 indicating acceptable multicollinearity. Statistical significance was defined as p<0.05. Model assumptions (linearity, homoscedasticity, normality of residuals) were also tested to validate the robustness of findings.
Ethical considerationsThis study was approved by the Research Ethics Committee with Medicines (CEIm) of the Gómez Ulla Central Defense Hospital (Approval Code: 3/23; Date: March 31, 2023). All procedures were conducted in accordance with the ethical principles set forth in the Declaration of Helsinki22 and complied with Spanish legislation on biomedical research and data protection.23
Participants were informed of their right to refuse or withdraw from the study at any point without affecting the continuity or quality of their medical care. No adverse events, coercion, or protocol deviations were recorded during the study.
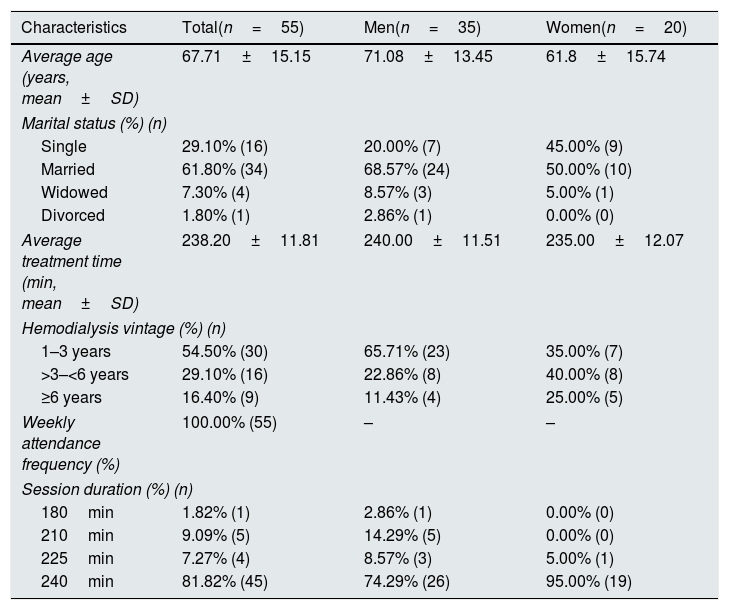
ResultsSociodemographic characteristics of the sample.The study sample comprised 55 patients undergoing HD, with a mean age of 67.71 years (SD=15.15). As shown in Table 1, most participants were married (61.8%), followed by single individuals (29.1%). Regarding educational attainment, 41.8% of the participants had completed basic education, 29.1% had completed high school.
General and gender-specific characteristics of hemodialysis patients.
| Characteristics | Total(n=55) | Men(n=35) | Women(n=20) |
|---|---|---|---|
| Average age (years, mean±SD) | 67.71±15.15 | 71.08±13.45 | 61.8±15.74 |
| Marital status (%) (n) | |||
| Single | 29.10% (16) | 20.00% (7) | 45.00% (9) |
| Married | 61.80% (34) | 68.57% (24) | 50.00% (10) |
| Widowed | 7.30% (4) | 8.57% (3) | 5.00% (1) |
| Divorced | 1.80% (1) | 2.86% (1) | 0.00% (0) |
| Average treatment time (min, mean±SD) | 238.20±11.81 | 240.00±11.51 | 235.00±12.07 |
| Hemodialysis vintage (%) (n) | |||
| 1–3 years | 54.50% (30) | 65.71% (23) | 35.00% (7) |
| >3–<6 years | 29.10% (16) | 22.86% (8) | 40.00% (8) |
| ≥6 years | 16.40% (9) | 11.43% (4) | 25.00% (5) |
| Weekly attendance frequency (%) | 100.00% (55) | – | – |
| Session duration (%) (n) | |||
| 180min | 1.82% (1) | 2.86% (1) | 0.00% (0) |
| 210min | 9.09% (5) | 14.29% (5) | 0.00% (0) |
| 225min | 7.27% (4) | 8.57% (3) | 5.00% (1) |
| 240min | 81.82% (45) | 74.29% (26) | 95.00% (19) |
n: number of participants or cases in a category; SD: standard deviation (a measure of variability).
The dialysis vintage was between 1 and 3 years in 54.5% of the cases, with a mean session duration of 238.20 minutes (SD = 11.81), and all participants attended three sessions per week.
Men represented 63.6% of the sample, with a higher mean age (71.08 years, SD=13.45), and the majority being married (68.6%). In terms of treatment history, 65.7% had been on HD for between one and three years, and 74.3% attended 240-min dialysis sessions.
Resilience and sociodemographic variablesParticipants demonstrated a moderate level of resilience. The mean resilience score was 74.02 (SD=13.99), with a median of 75. Normality was confirmed (p=0.096).
A Spearman's rank-order correlation was performed to explore associations between resilience (dependent variable) and various sociodemographic and clinical factors. A statistically significant moderate positive correlation was observed between resilience and educational level (ρ=0.307, p=0.023), indicating that higher educational attainment is associated with greater resilience.
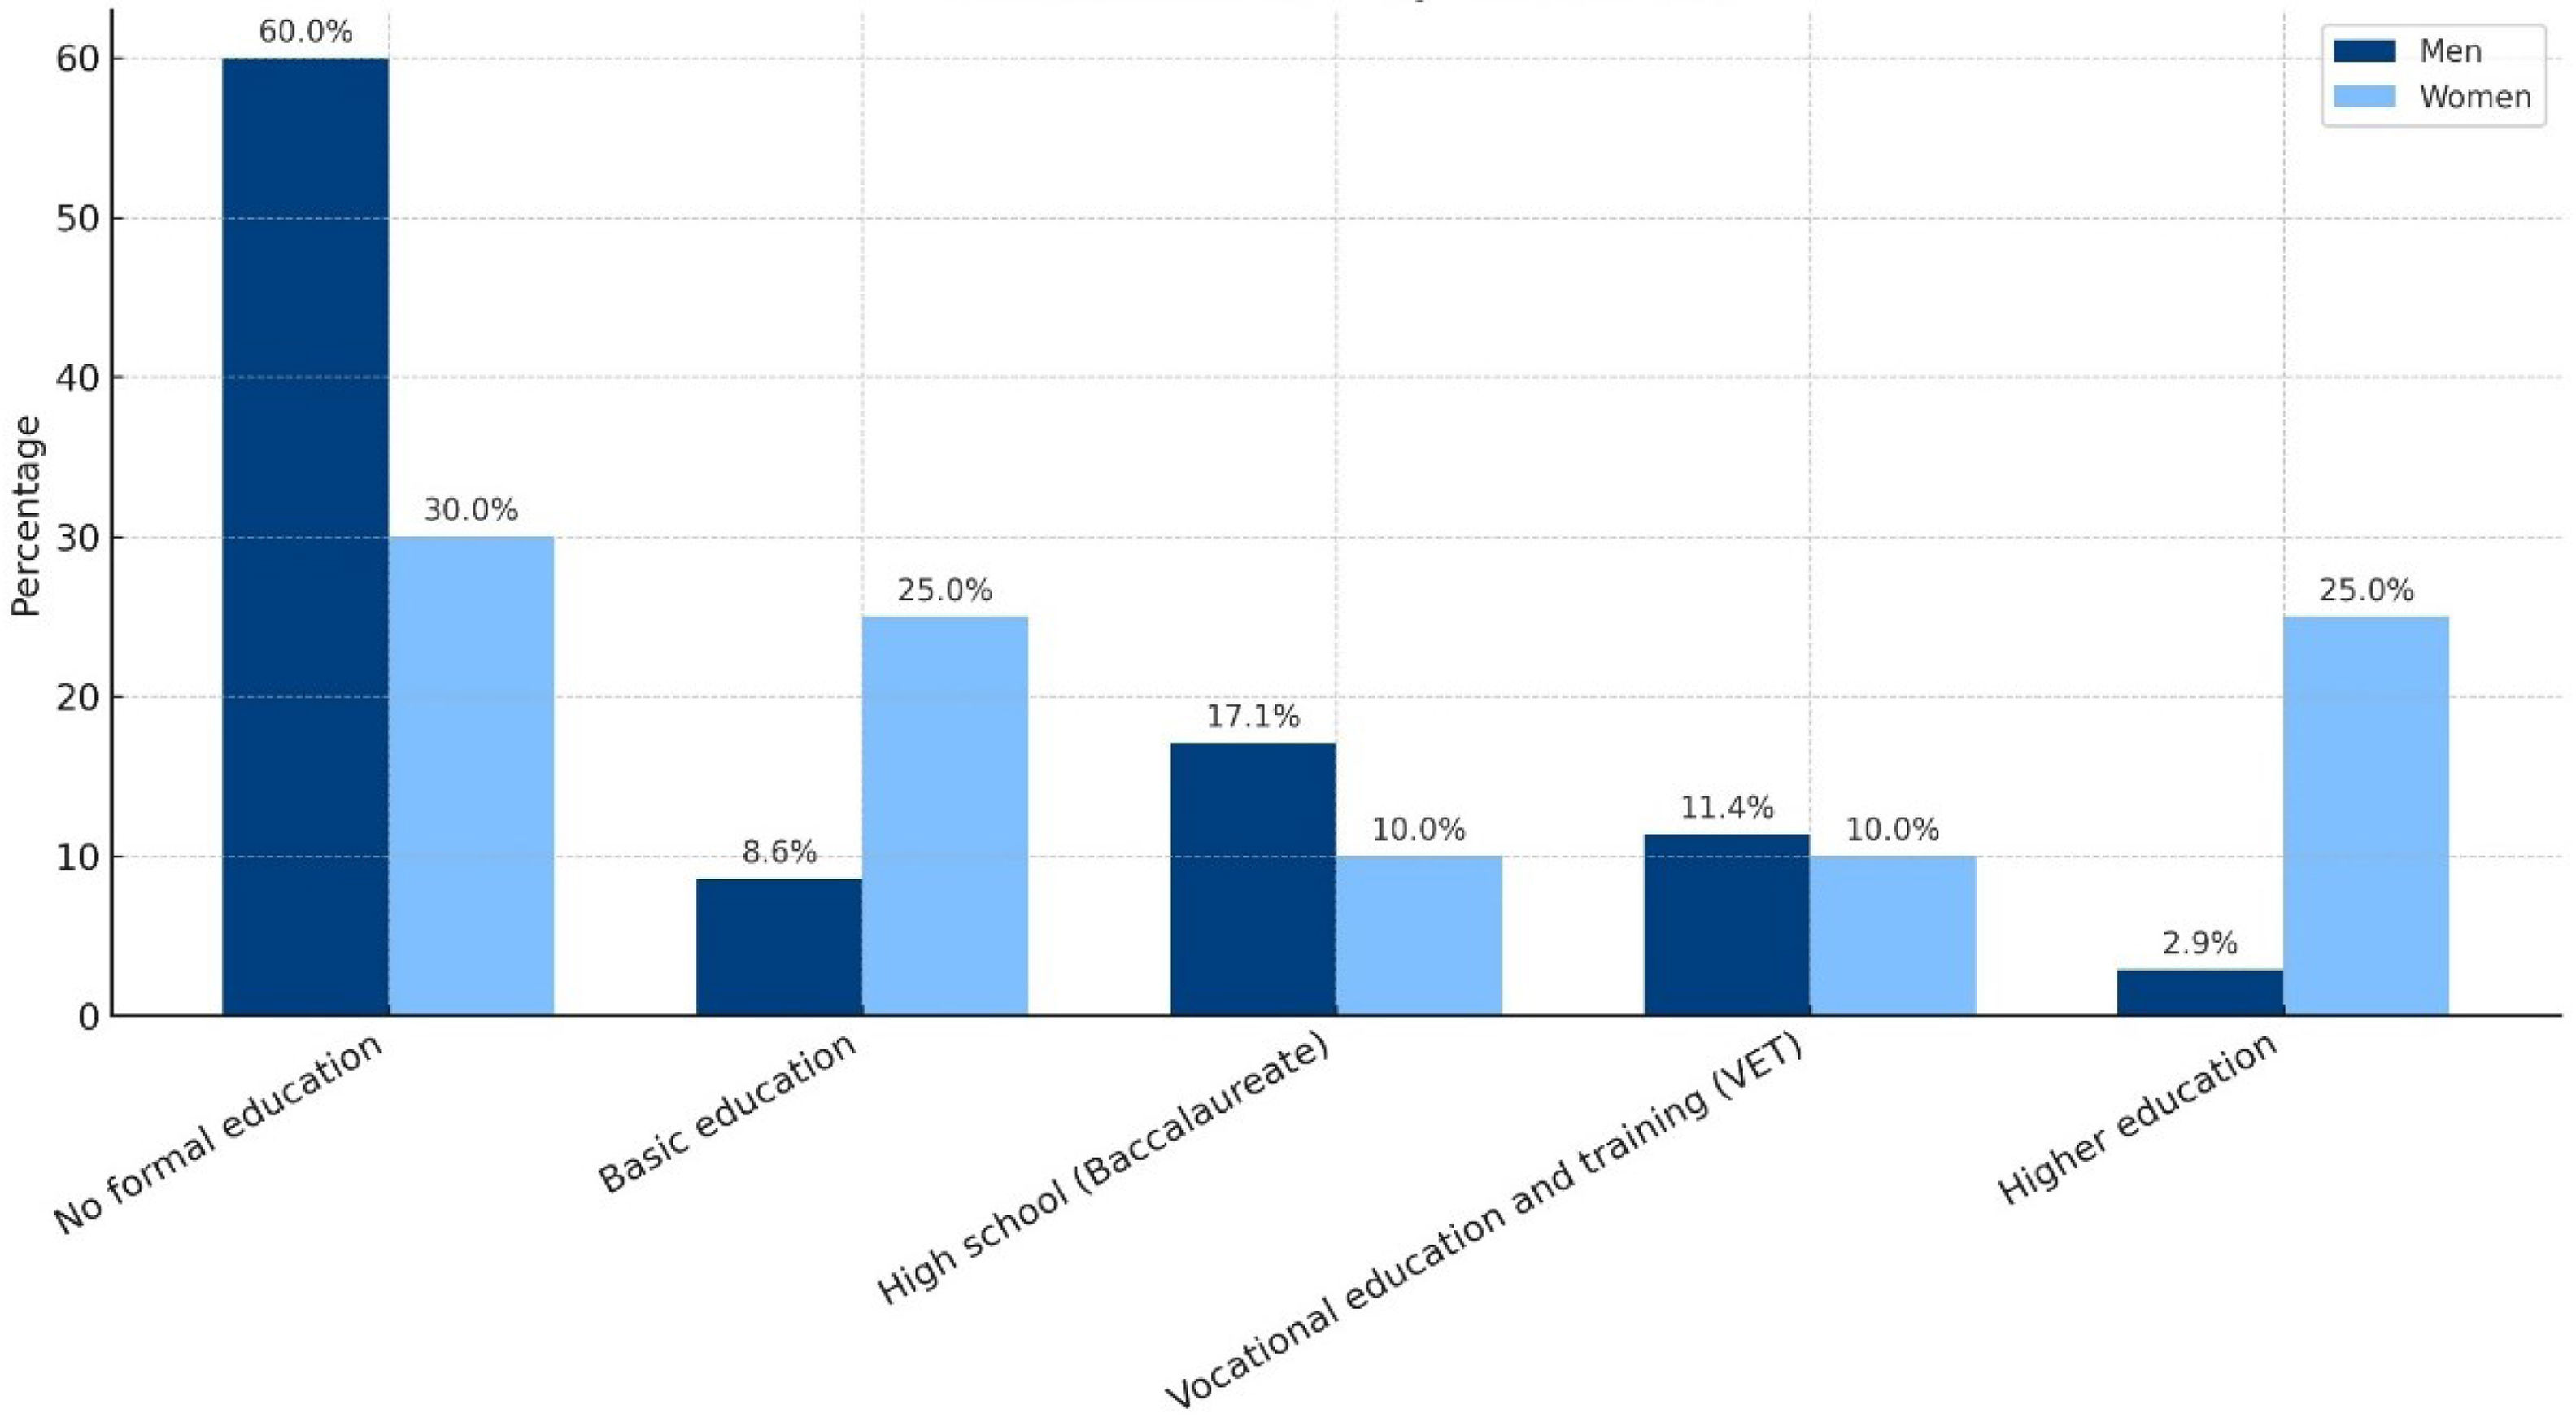
Men were more frequently represented in the lower educational categories, including no formal education, whereas women showed a more balanced distribution across basic and higher educational levels (Fig. 2).
Regression analysis: limited predictive value of clinical and sociodemographic variables
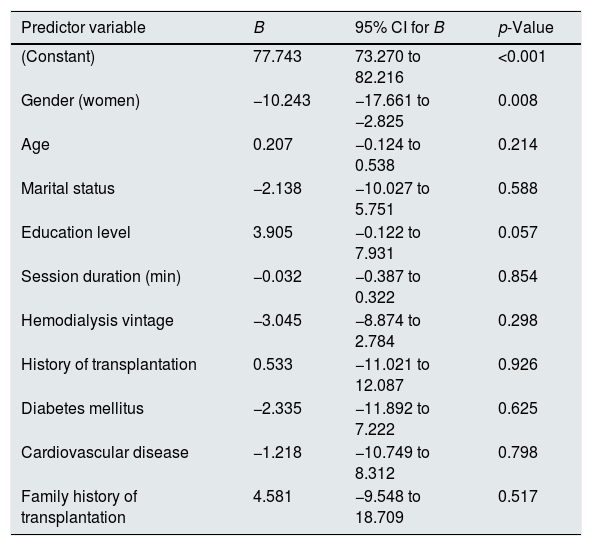
Among the individual predictors, gender and educational level showed the strongest associations with resilience. Being a woman was associated with a 10.24-point lower resilience score (p=0.008), accounting for 12.6% of the explained variance (Table 2).
Univariate screening and multivariate linear regression analysis of resilience.
| Predictor variable | B | 95% CI for B | p-Value |
|---|---|---|---|
| (Constant) | 77.743 | 73.270 to 82.216 | <0.001 |
| Gender (women) | −10.243 | −17.661 to −2.825 | 0.008 |
| Age | 0.207 | −0.124 to 0.538 | 0.214 |
| Marital status | −2.138 | −10.027 to 5.751 | 0.588 |
| Education level | 3.905 | −0.122 to 7.931 | 0.057 |
| Session duration (min) | −0.032 | −0.387 to 0.322 | 0.854 |
| Hemodialysis vintage | −3.045 | −8.874 to 2.784 | 0.298 |
| History of transplantation | 0.533 | −11.021 to 12.087 | 0.926 |
| Diabetes mellitus | −2.335 | −11.892 to 7.222 | 0.625 |
| Cardiovascular disease | −1.218 | −10.749 to 8.312 | 0.798 |
| Family history of transplantation | 4.581 | −9.548 to 18.709 | 0.517 |
Note. B: unstandardized regression coefficient; CI: confidence interval. All variables were entered simultaneously into the multivariate model.
Overall diagnostic checks indicated no relevant violations of regression assumptions.
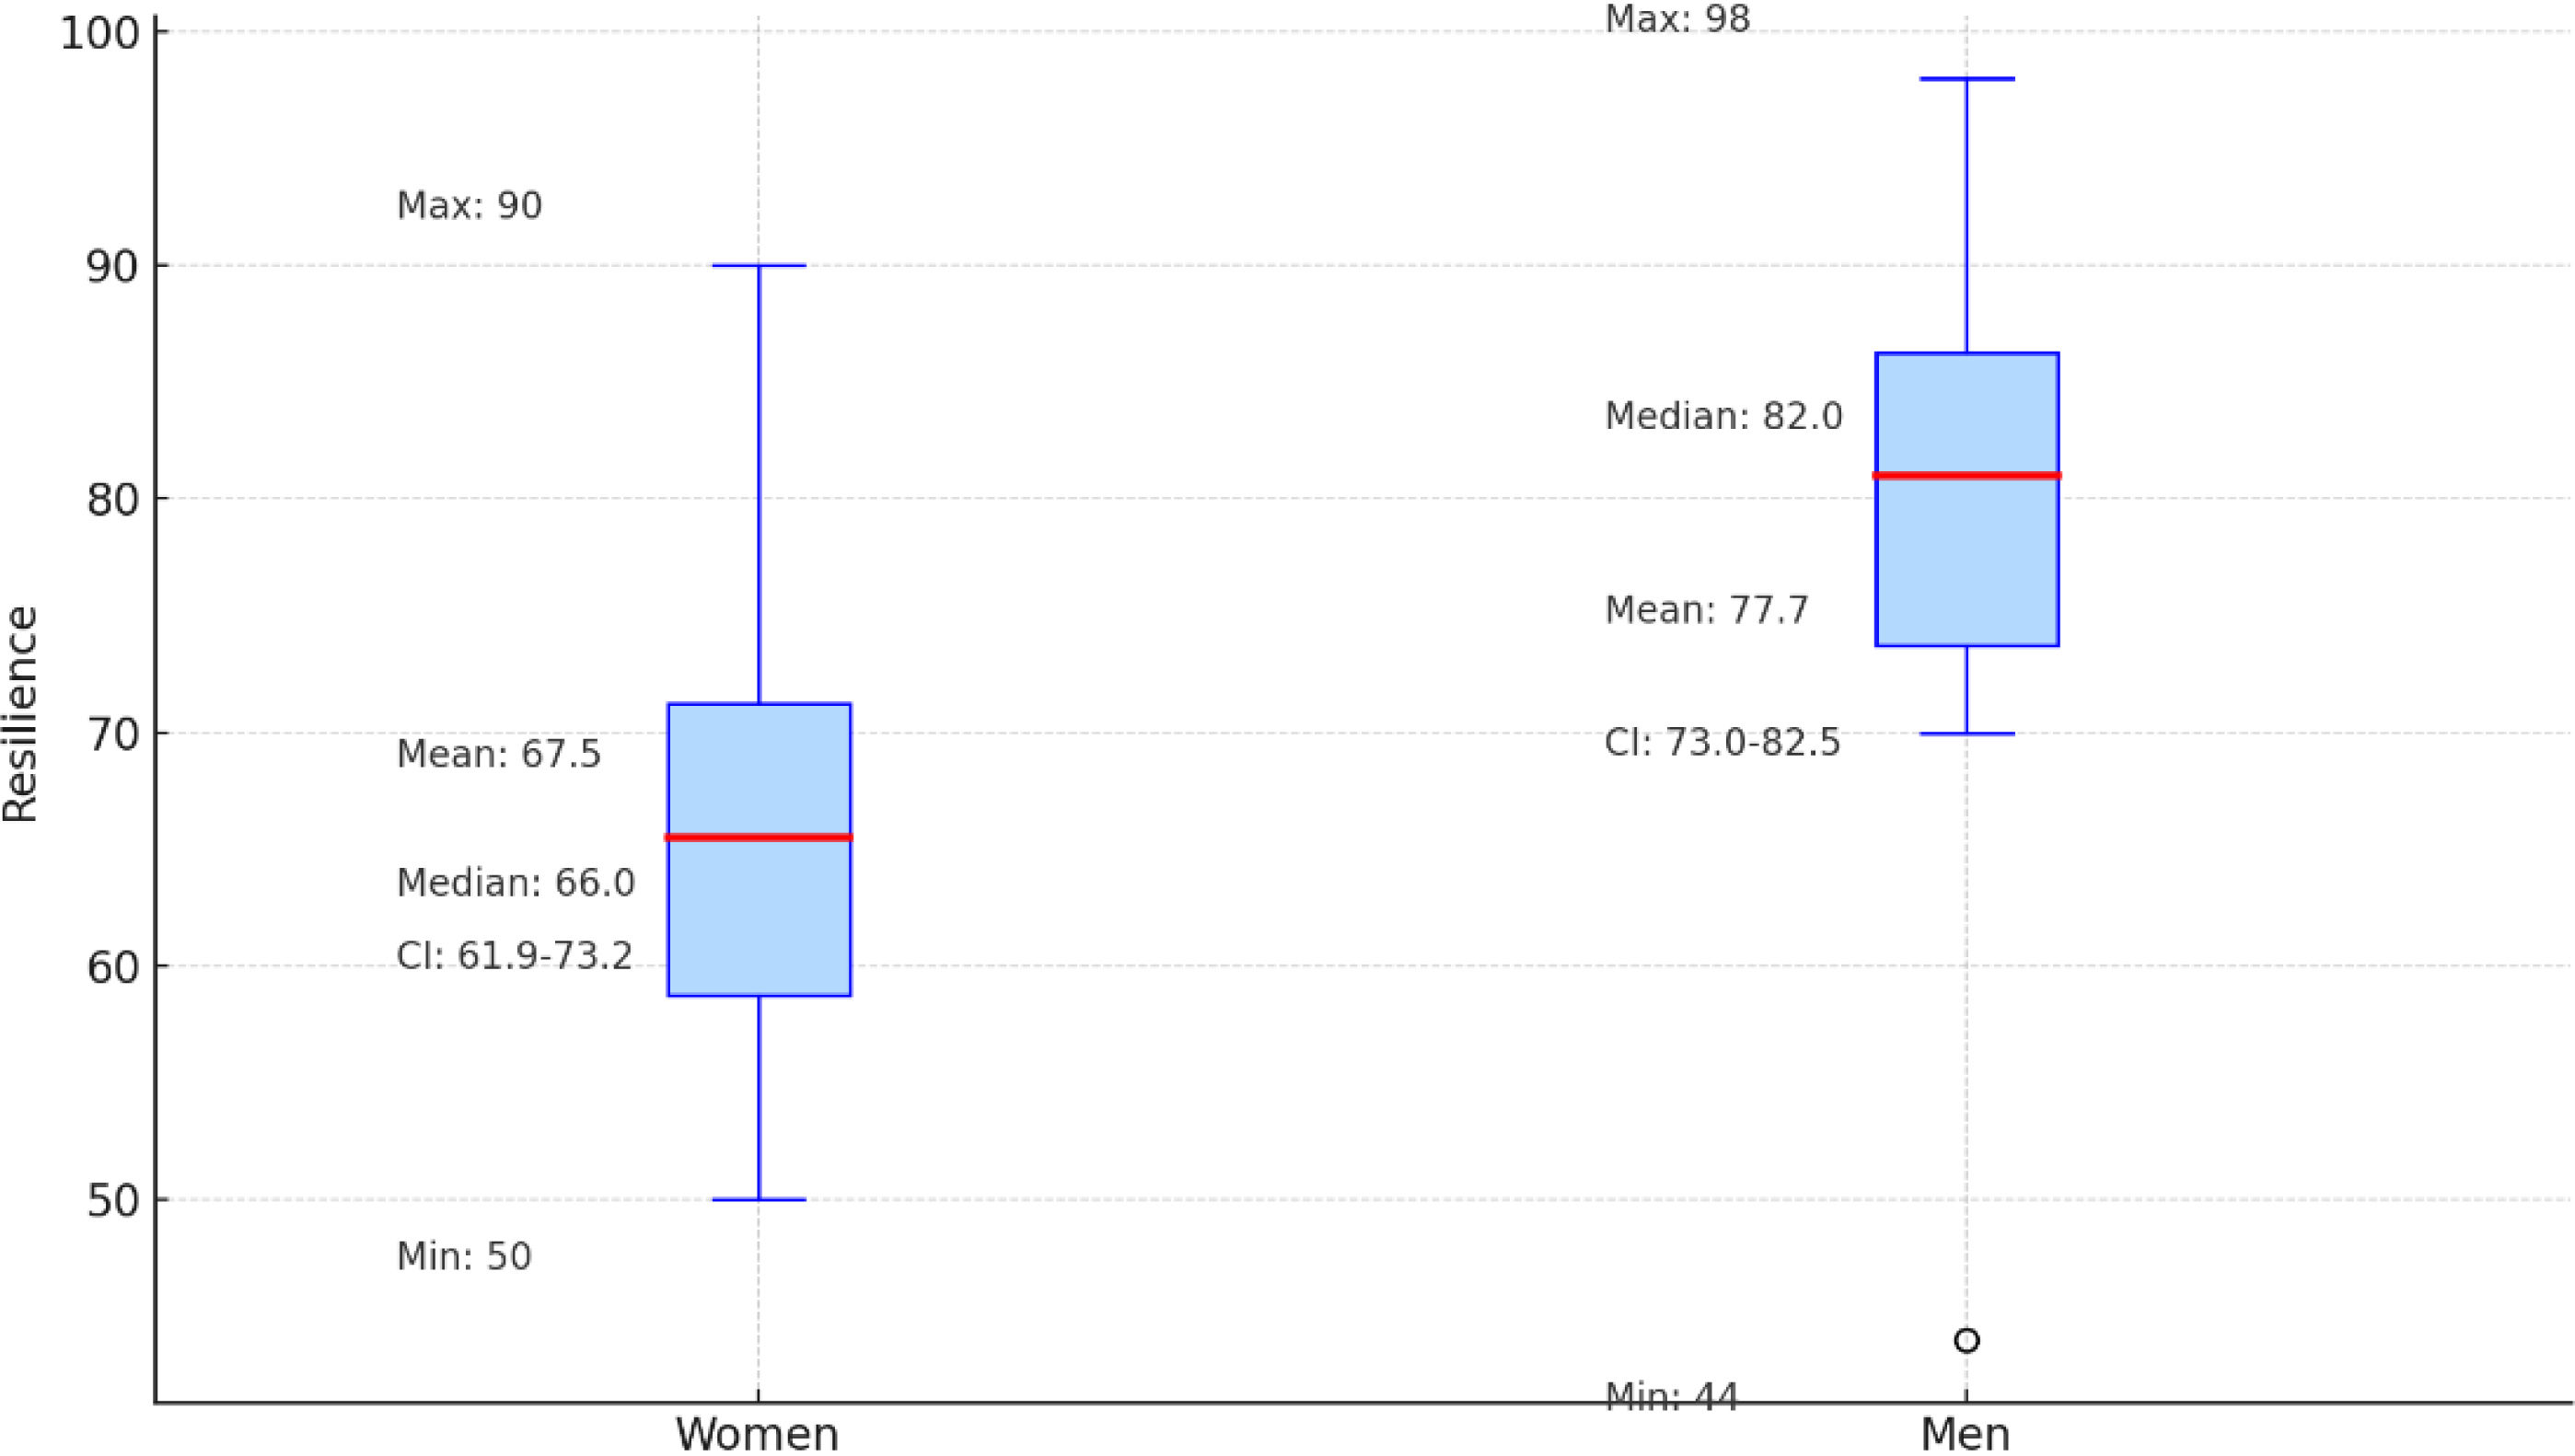
Resilience depending on genderMen exhibit both higher resilience levels and greater score variability, whereas women's scores cluster more tightly around moderate values (Fig. 3).
Discussion
This study found that patients with ESRD undergoing HD demonstrate moderate resilience, consistent with international evidence highlighting its protective role against anxiety and depression.2,24–26 These findings support a multifactorial understanding of resilience shaped by psychological traits, social support, and cultural context, with implications for patient-centered care.
A key result was higher resilience scores in men. Prior research suggests that men more frequently adopt problem-focused coping strategies, whereas women experience greater psychosocial burden related to caregiving roles and emotional labor.9,25 Evidence in CKD indicates that these differences are largely driven by sociocultural gender roles rather than biological factors alone.8,9,27 In Mediterranean contexts such as Spain, strong family-centered care models coexist with highly gendered caregiving responsibilities,28,29 which may partially explain the observed patterns. Dyadic studies further show that family resilience and adaptive coping are associated with lower caregiver burden and better psychological adjustment,30,31 underscoring the relevance of relational dynamics.
Educational level also correlated positively with resilience. Even moderate educational attainment may enhance health literacy, proactive coping, and engagement in care, consistent with prior findings linking education to better psychological well-being, adherence, and social functioning.32–35 Emerging evidence suggests potential gender×education interactions in shaping emotional adjustment,36,37 as well as gender-specific pathways through which social support influences resilience.38,39
No significant associations were observed between resilience and age, marital status, comorbidity burden, or vascular access type. Discrepancies with previous studies may reflect methodological and contextual differences.8,40 Notably, perceived illness burden may exert greater influence than objective clinical indicators.19 Resilience should also be conceptualized as dynamic: early adaptation to dialysis may temporarily strengthen resilience, whereas prolonged treatment exposure may erode coping resources.8,9,19
Across studies, social and family support consistently emerge as central determinants of resilience, self-efficacy, and quality of life.8,37,38 Dialysis care should therefore incorporate assessment of support networks and consider family-focused and culturally sensitive interventions.37,38,40 The modest explanatory power of the multivariate model (22%) further indicates that additional determinants – such as coping style, spirituality, self-compassion, socioeconomic position, health literacy, and patient–provider communication – require exploration in future research.19,35,40,41
Strengths and limitations of the studyThis study provides clinically meaningful insights into psychological resilience in patients with ESRD undergoing HD, particularly regarding sociodemographic and sex-related predictors. Methodological rigor was supported by the use of the validated RS-14 and by including patients with at least 12 months on HD, minimizing early adaptation bias. The integration of a contemporary framework distinguishing biological sex from gender enhances interpretability, and the use of complementary statistical techniques strengthened analytical robustness.
However, the cross-sectional design precludes causal inference. The small, homogeneous, single-center sample (n=55), recruited through consecutive nonprobabilistic sampling, limited statistical power and external validity. The unbalanced sex distribution may have reduced sensitivity for subgroup analyses. Relevant dimensions such as gender identity, caregiving roles, economic autonomy, discrimination, social support structure, coping style, spirituality, and self-efficacy were not assessed. Although the RS-14 is psychometrically robust, it does not capture gender-sensitive domains, which may partly explain the modest explanatory power of the regression model.
Clinical perspectives and future directionsThese findings highlight the need for integrative approaches addressing both psychological and social determinants of resilience in HD care. Given the limited variance explained by the current model, future research should examine interventions targeting adaptive coping, self-care behaviors, and patient education, which have been associated with improved resilience, adherence, and psychological well-being.24,32
Longitudinal, multicenter studies are warranted to explore resilience trajectories across diverse caregiving and institutional contexts. Evidence supports the effectiveness of family-focused psychoeducation, structured coping-skills training, caregiver-support programs, and educational initiatives in improving psychological outcomes, self-efficacy, and adherence in chronic kidney disease populations.40–43
Adaptive coping strategies – such as problem-solving, emotional regulation, and seeking social support – facilitate psychological adjustment to HD, whereas maladaptive strategies are linked to greater distress and poorer adherence.24,32 Educational and psychosocial interventions targeting these mechanisms have demonstrated benefits in strengthening resilience and reducing emotional burden.44–46 Additionally, self-care behaviors, including adherence to dietary and medication regimens, are positively associated with quality of life and resilience.47 Multidisciplinary educational programs have shown improvements in disease understanding, self-efficacy, decision-making, and clinical outcomes, including reduced hospitalizations.48,49 Integrating educational and psychosocial strategies into routine nephrology care may therefore enhance resilience and optimize long-term outcomes.49,50
ConclusionsThis preliminary study suggests that patients with ESRD undergoing HD present moderate levels of psychological resilience, with higher scores observed in men and in individuals with higher educational attainment. These associations should be interpreted with caution given the limited sample size, the single-center design, and the absence of key psychosocial and contextual variables in the analysis.
The findings underscore the need for larger, adequately powered multicenter studies incorporating multidimensional gender measures, broader sociodemographic and contextual indicators, and detailed assessments of social and family support to clarify the mechanisms shaping resilience in hemodialysis populations. Such studies are essential to clarify the mechanisms shaping resilience in HD populations and to verify whether the patterns observed here are consistent across different settings.
Future research should also explore targeted interventions aimed at strengthening resilience in vulnerable groups, particularly programs integrating psychosocial support, caregiver engagement, and education-based strategies that address gendered and sociocultural determinants of emotional adaptation.
CRediT authorship contribution statementConcept, GMZF; methodology, GMZF, JDF, VFA, RJEDLR, and RFC; software, GMZF; validation, GMZF, JCDF, VFA, EIC, RJEDLR, RFC, and RFC; formal analysis, GMZF, JDF, EIC, RJEDLR, and RFC; research, GMZF, JDF, VFA, EIC, and RFC; resources, GMZF and JDF; data curation, GMZF, JDF, VFA, and EIC; writing of the original draft, GMZF, JDF, VFA, and EIC; writing, revision and edition, GMZF and RJEDLR; visualization, GMZF, JDF, VFA, EIC, and RFC; supervision, GMZF. All the authors have read and accepted the final published version of the manuscript.
Institutional review board statementThe ethical review was approved by the Institutional Review Board (Code: 3/23) on March 31, 2023.
Informed consent statementInformed consent was obtained in writing from all patients prior to inclusion in this study (including the publication of images).
FundingThis research has not received external funding.
Conflict of interestThe authors declare no conflicts of interest that could have influenced the results or discussion of this article. This research received no specific support from public sector agencies, commercial entities, or nonprofit organizations.
This study is part of the doctoral thesis entitled “Resilience Levels in Patients with Chronic Kidney Disease Undergoing Renal Replacement Therapy via Hemodialysis: Associations with Depression, Anxiety, Stress, and Quality of Life”, presented in the Doctoral Programme in Medicine and Public Health at the University of Granada, under the supervision of Prof. Dr. Rafael Fernández Castillo.
The following are the supplementary data to this article:





