



Chronic kidney disease (CKD) is a growing global health problem associated with high cardiovascular risk and rising healthcare costs. International clinical guidelines and scientific societies consistently recommend integrated care models between primary care (PC) and nephrology to improve early detection, ensure appropriate referral, and optimize long-term management of CKD. However, large-scale and sustained implementation of such models remains limited.
MethodsWe describe the 25-year experience of an integrated CKD care program in the Barcelona Right Health District (AP AIS Dreta-Fundació Puigvert), a collaborative initiative between nephrology and PC. The program was developed through joint professional education, shared referral protocols, virtual consultations, patient-focused interventions, a multidisciplinary clinical group, and continuous evaluation. The program was evaluated using clinical indicators, activity data, and patient registries.
ResultsCKD prevalence in the district increased from 2.3% in 2011 to 6.9% in 2024, with a 25% rise in registered patients over the last decade. Prescriptions of ACE inhibitors or ARB nearly doubled, while chronic NSAID use fell below 2%. Blood pressure control was achieved in over 60% of hypertensive patients. Virtual consultations expanded from 145 in 2016 to 954 in 2024, resolving 79% of queries without the need for face-to-face visits. Patient-centered initiatives and professional training received satisfaction ratings above 4.7/5, and the program has been nationally recognized for its innovation in CKD care.
ConclusionThe AP AIS Dreta-Fundació Puigvert program shows that sustained collaboration between nephrology and PC can be consolidated over time within a real-world territorial setting, supporting coordinated CKD detection, management, and follow-up. Its long-standing experience and multidisciplinary structure make it a relevant model for integrated CKD care, with potential for replication in other healthcare settings. Future priorities include evaluating cost-effectiveness and demonstrating improvements in clinical outcomes to strengthen long-term sustainability.
La enfermedad renal crónica (ERC) es un problema creciente de salud global, asociado a un elevado riesgo cardiovascular y a un aumento de los costes sanitarios. Las guías clínicas internacionales y las sociedades científicas recomiendan la implementación de modelos de atención integrada entre atención primaria (AP) y nefrología para mejorar la detección precoz, garantizar una derivación adecuada y optimizar el manejo a largo plazo de la ERC. Sin embargo, la implementación generalizada y sostenida de estos modelos sigue siendo limitada.
MétodosDescribimos la experiencia de 25 años de un programa de atención integrada a la ERC en el Área Integral de Salud Barcelona Dreta (AP AIS Dreta-Fundació Puigvert), una iniciativa colaborativa entre nefrología y AP. El programa se desarrolló mediante formación conjunta de profesionales, protocolos compartidos de derivación, consultas virtuales, intervenciones centradas en el paciente, un grupo clínico multidisciplinar y evaluación continua. El programa se evaluó mediante indicadores clínicos, datos de actividad y registros de pacientes.
ResultadosLa prevalencia de ERC en el territorio aumentó del 2,3% en 2011 al 6,9% en 2024, con un incremento del 25% en el número de pacientes registrados durante la última década. Las prescripciones de IECA o ARA-II prácticamente se duplicaron, mientras que el uso crónico de AINE descendió por debajo del 2%. Se alcanzó el control de la presión arterial en más del 60% de los pacientes hipertensos. Las consultas virtuales aumentaron de 145 en 2016 a 954 en 2024, resolviendo el 79% de las consultas sin necesidad de visitas presenciales. Las iniciativas centradas en el paciente y la formación de profesionales obtuvieron puntuaciones de satisfacción superiores a 4,7/5, y el programa ha recibido reconocimiento nacional por su innovación en la atención a la ERC.
ConclusiónEl programa AP AIS Dreta-Fundació Puigvert muestra que la colaboración sostenida entre nefrología y AP puede consolidarse en el tiempo en un entorno territorial real, favoreciendo la detección, el manejo y el seguimiento coordinados de la ERC. Su larga trayectoria y estructura multidisciplinar lo convierten en un modelo relevante de atención integrada a la ERC, con potencial de replicación en otros entornos sanitarios. Las prioridades futuras incluyen evaluar su coste-efectividad y demostrar mejoras en los resultados clínicos para reforzar su sostenibilidad a largo plazo.
Chronic kidney disease (CKD) affects approximately 10% of the global adult population, an estimated 850 million, representing a major public health challenge.1–3 Closely linked to diabetes, hypertension, and cardiovascular disease, CKD progression often leads to renal replacement therapy, consuming a substantial share of healthcare resources.4,5 In Western Europe, where life expectancy is long, CKD will become the third cause of death within 25 years.6 In 2025, the World Health Organization (WHO) recognized kidney health as a global non-communicable disease (NCD) priority, alongside cardiovascular, pulmonary, oncological, and metabolic disorders, in response to its growing prevalence, mortality, and economic burden.7–9
Fragmented care across health system levels contributes to delayed diagnosis, suboptimal management, inappropriate medication use, and poor coordination between providers. Limited nephrology training for primary care (PC) teams further exacerbates these gaps. Yet PC plays a critical role as the first point of contact for patients: it performs initial screening, initiates nephroprotective treatment, and ensures strict control of cardiovascular risk factors. Although integrated care models that promote collaboration between nephrology and PC are widely recommended, their implementation in real-world practice remains heterogeneous.10,11
Spain has a universal, tax-funded healthcare system in which PC is the cornerstone of prevention and chronic disease management. In Catalonia, services are organized into Integral Health Areas (Àrees Integrals de Salut, AIS), which coordinate hospitals and PC teams within a defined territory to ensure continuity of care. These services are coordinated and funded by the Catalan Health Service (CatSalut), the public agency responsible for health planning and healthcare provision in Catalonia. The Barcelona Right Health District (AP AIS Dreta-Fundació Puigvert) has developed an early and long-standing integrated CKD care in Spain.12 Serving more than 425,000 residents across 16 PC teams, this district has maintained a close 25-year collaboration with its referral nephrology center, the Fundació Puigvert. The program combines joint professional education, shared care pathways, patient-focused initiatives, and systematic evaluation.
This article describes the program's development, activities, and outcomes, highlighting its strengths, limitations, and potential for replication. It serves as a practical example of how sustained local collaboration can support integrated CKD care in routine clinical practice.
Methods: program descriptionStudy design and settingWe describe the development, implementation, and evaluation of the integrated CKD care model in the Barcelona Right Health District (AP AIS Dreta-Fundació Puigvert). This program serves a population of 428,738 inhabitants through a network of 16 PC teams: nine from the Catalan Institute of Health (the main public provider of PC services) and seven from other contracted entities (Fig. 1). Fundació Puigvert serves as the district's referral center for nephrology. It is a specialized, high-complexity university hospital embedded within the tertiary-level Hospital de la Santa Creu i Sant Pau, with a focus on nephrology, urology, andrology, and reproductive medicine.
Program objectives
The program's main goal is to ensure continuity and high-quality care for CKD patients through close collaboration between PC and nephrology. Specific objectives include early detection of CKD and reversible causes; creation of shared clinical pathways; optimization of treatment to slow disease progression and manage cardiovascular risk; reduction of unnecessary visits and duplicate testing; reinforcement of multidisciplinary coordination; promotion of professional training and innovation; and implementation of patient-focused activities. The program also aims to monitor selected clinical and organizational outcomes, resource optimization, and the creation of a potentially scalable model applicable to other chronic conditions.
Implementation processCollaboration between nephrology and PC began in the late 1990s with joint educational sessions. These efforts gradually expanded to include shared clinical protocols, professional and patient education programs, and joint strategic planning. Since 2018, a multidisciplinary working group has coordinated the program through regular meetings. Implementation has been incremental, driven by growing trust among professionals and the progressive adoption of tools such as the PC electronic health record (PC-EHR). In-person nephrology care was delivered through established outpatient clinics, including general nephrology and CKD-related subspecialty areas. Within this framework, virtual consultation functioned as a complementary clinical and decision-support tool between PC and nephrology. It was mainly used by PC physicians to discuss diagnostic, therapeutic, and test-interpretation issues in CKD patients. Depending on the clinical situation, cases could be managed remotely or referred for in-person outpatient nephrology assessment or, when clinically indicated, urgent care evaluation. In addition, information from publicly funded activities is progressively being integrated into the Catalan Shared Health Record, thereby facilitating continuity of care across settings, although interoperability between providers and information systems remains incomplete. Fig. 2 summarizes the chronological integration of activities, from initial initiatives to structured strategic plans.
Evaluation and monitoring
Systematic evaluation was formalized through strategic plans introduced in 2018, which established clear objectives, indicators, and continuous improvement cycles. Monitoring is based on routine clinical data, including diagnostic coding and patient registration, clinical follow-up, care transitions, and patient-centered initiatives. Results are reviewed in multidisciplinary meetings to guide ongoing development.
Indicators have been incorporated progressively, reflecting improvements in data availability and health information systems. In 2024, the multidisciplinary group defined a comprehensive set of 45 indicators, categorized into three domains: structural parameters, healthcare quality indicators, and satisfaction metrics. These include measures from the local CKD care pathway, the Information Systems for PC Services (SISAP) of the Catalan Health Institute, and recommendations from nephrology societies.13 However, because data capture and integration across providers and information systems were not uniform over time, not all indicators were consistently available throughout the study period, and the retrieval and territorial consolidation of some CKD indicators remained challenging. The full set of indicators and longitudinal data for selected measures are presented in the results section and in Figs. 3 and 4.


During most of the study period, CKD detection and diagnostic coding in routine care were not supported by automated EHR alerts or formal audit-feedback circuits specifically targeting CKD registration. More recently, SISAP incorporated an informative indicator based on persistent analytical CKD criteria.
Ethics and data protectionAll program activities complied with current ethical and data protection standards. Clinical data used for evaluation were anonymized and drawn from routine public healthcare records, without individual identifiers or need for formal ethics approval.
Results and outcomesActivitiesThe program has progressively implemented a wide range of activities (see Fig. 2).
- •
Professional training has included lectures, annual meetings, workshops, and hospital rotations. In 2025, infographic materials were developed to support decision-making and address high staff turnover in PC, made accessible via the PC-EHR and the Fundació Puigvert website.
- •
Shared clinical pathways were established, including weekly nephrologist review of referrals; informed review of cases via the Catalan Shared Health Record for referral requests not requiring an in-person visit; and contributions to the local CKD care pathway, the Catalan CKD consensus, and the Catalan therapeutic harmonization guidelines.
- •
Coordination is led by a multidisciplinary working group of over 30 professionals from nephrology, PC, nursing, clinical laboratory, epidemiology, and health management, with input from endocrinology, cardiology, and geriatrics when needed. Clinical consultations evolved from joint case reviews and email-based virtual consultations to full PC-EHR integration, with reference nephrologists assigned to each PC team. Virtual consultation became an established coordination pathway between PC and nephrology, supporting case discussion, diagnostic and therapeutic decision-making, and referral prioritization across care levels.
- •
The program has received recognition through congress presentations, publications, and four institutional awards for quality and innovation in CKD care.
- •
Patient-centered initiatives include the Living with Kidney Disease program, the CatSalut Expert Patient Program, and a mentoring program for advanced CKD.
- •
Strategic planning has been structured into three consecutive cycles (2018–2021, 2022–2024, 2025–2027), each with continuous monitoring.
Systematic evaluation has been a core component of the program since 2018, guided by strategic planning and multidisciplinary review.
- •
Detection and registration. The CKD register in the district tripled between 2011 and 2017, increasing from 2.38% to 6.06%. By 2024, prevalence had further risen to 6.92%, reflecting a 25% growth in registered cases over the last decade, with a total of 18,340 adults diagnosed with CKD across the district. A laboratory-based algorithm using CKD criteria (≥2 eGFR values <60ml/min/1.73m2 and/or ≥2 urinary albumin-to-creatinine ratios >30mg/g, persisting for more than three months), implemented by SISAP, identified 1397 additional patients who met diagnostic criteria but had no registered CKD diagnosis. Periodic review of discrepancies between patients meeting laboratory criteria for CKD and those with a registered diagnosis would be advisable to ensure alignment between clinical records and objective data. Such reviews could help identify both under- and over-registration of CKD cases. This recorded prevalence should be interpreted with caution, as territorial estimates may be affected by incomplete capture of residents receiving care outside the publicly funded network and by limitations in data integration across settings.
- •
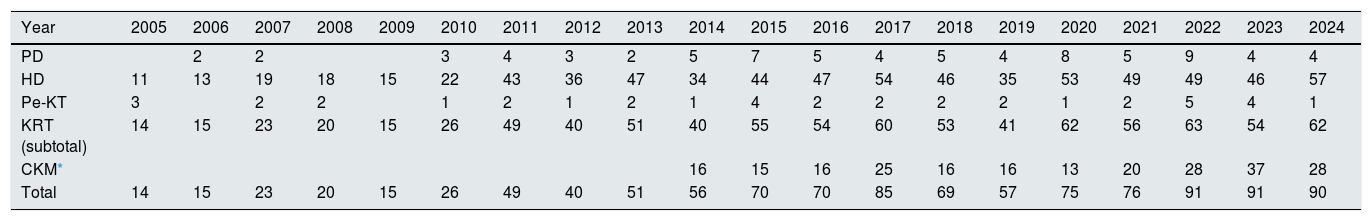
Clinical management. Virtual consultations increased from 145 in 2016 to 954 in 2024, with 79% resolved without face-to-face visits. When case-level data became available, this activity corresponded to 707 cases in 2023 (790 consultations) and 885 cases in 2024 (954 consultations), reflecting the growing use of this coordination pathway in routine care. During the same period, the number of first in-person outpatient visits in the nephrology department increased progressively from 778 in 2016 to 1576 in 2024, reflecting the broader clinical activity of the service. Referrals from PC within the territory accounted for approximately 40–55% of these visits, with the remainder originating from hospital specialists both within and outside the reference area. Control rates showed 61.2% of hypertensive patients with adequate blood pressure control, 38.4% of diabetic patients with HbA1c <7%, and only 13.5% of patients with dyslipidemia reaching LDL ≤70mg/dL, indicating suboptimal lipid control. Unfortunately, just one-third of patients had an albuminuria test registered in the PC-EHR in the last year. Therapeutic trends improved: ACE inhibitors/ARB prescriptions nearly doubled (82% increase), chronic NSAID use declined to 1.8%, and SGLT2 inhibitors were introduced in 2024. To provide contextual information on advanced CKD outcomes, we analyzed the annual number of patients from the reference territory initiating kidney replacement therapy (KRT), as well as those managed with conservative kidney management (CKM) (Table 1). The number of patients initiating KRT increased over time with interannual variability. CKM, introduced in 2014, showed marked year-to-year fluctuations with higher values in some recent years. Overall, the total number of patients managed with either KRT or CKM increased over time, reaching a plateau in the last years of the study period.
Table 1.Annual number of patients from the reference territory initiating kidney replacement therapy and conservative kidney management, 2005–2024.
Year 2005 2006 2007 2008 2009 2010 2011 2012 2013 2014 2015 2016 2017 2018 2019 2020 2021 2022 2023 2024 PD 2 2 3 4 3 2 5 7 5 4 5 4 8 5 9 4 4 HD 11 13 19 18 15 22 43 36 47 34 44 47 54 46 35 53 49 49 46 57 Pe-KT 3 2 2 1 2 1 2 1 4 2 2 2 2 1 2 5 4 1 KRT (subtotal) 14 15 23 20 15 26 49 40 51 40 55 54 60 53 41 62 56 63 54 62 CKM* 16 15 16 25 16 16 13 20 28 37 28 Total 14 15 23 20 15 26 49 40 51 56 70 70 85 69 57 75 76 91 91 90 CKM: conservative kidney management; HD: hemodialysis; KRT: kidney replacement therapy; PD: peritoneal dialysis; Pe-KT: pre-emptive kidney transplant. KRT includes HD, PD and Pe-KT.
- •
Complexity and transitions. A total of 26.2% of CKD patients were classified as complex or advanced chronic patients. Among them, 95.2% of hospital discharges included structured discharge planning to ensure continuity of care with PC services.
- •
Resources and capacity. In 2024, nephrology care in the district was provided by a total of 29 nephrologists (24 from Fundació Puigvert and 5 from two community-based dialysis centers) and 117 specialized nurses (67 hospital-based and 50 from the same dialysis centers), corresponding to ratios of one nephrologist per 632 CKD patients and one nurse per 156. A core team of five nephrologists from Fundació Puigvert led the integrated CKD care program, with varying levels of involvement; one of them coordinated the nephrology component in close collaboration with the program's PC coordinator. All 16 PC teams had an assigned nephrology consultant and a designated PC physician, with access to virtual consultations with their corresponding nephrologist. In addition, the 16 PC teams included 267 physicians and 273 nurses, serving 428,738 inhabitants, reflecting balanced PC staffing and providing the foundation for the district's integrated CKD care network. In parallel, virtual nursing consultations for PC nurses were being progressively implemented; however, only 6.25% of teams had a designated PC nurse or access to this service.
- •
Training and coordination. A total of 151 PC physicians received accredited hospital training, complemented by 90 workshops (average annual participation: 239 professionals) and 26 joint annual meetings since 1998, with 160 participants in the most recent edition.
- •
Patient programs. Ten editions of the Living with Kidney Disease program have been held, and a mentoring program was launched for patients with advanced CKD. In addition, our integrated CKD care team was selected by CatSalut to develop the CKD-specific version of the Expert Patient Program. The team led the design of the educational content, conducted pilot testing and evaluation, and made the program available to centers across Catalonia.
- •
Satisfaction. Surveys showed consistently high ratings: 4.7–4.8/5 for professional training activities and 4.8–4.9/5 for patient programs.
Taken together, these findings reflect the progressive consolidation of integrated CKD care in AP AIS Dreta-Fundació Puigvert, while also identifying persistent areas for clinical improvement.
DiscussionIntegrating care for CKD between primary and specialty care is a widely recommended strategy to address the growing burden of the disease.8,11,14 The integrated CKD care program in the AP AIS Dreta-Fundació Puigvert represents a long-term comprehensive response to the complex challenges of CKD management in real-world practice.
The program's distinct value lies in its capacity to support coordinated care and more efficient use of resources within a multidisciplinary and adaptable framework. Over the past decade, CKD diagnoses rose by 25%, enabling earlier protective interventions. Resource optimization is reflected in the rise in nephroprotective therapy prescribing and the effective resolution of 79% of virtual consultations, which likely reduced the need for additional visits and contributed to more efficient nephrology care. Crucially, the model has evolved through periodic pathway updates, continuous education for professionals and patients, and structured three-year strategic plans, with external recognition underscoring its maturity. As a contextual measure of advanced CKD burden, data from the reference territory show that both the number of patients initiating KRT and those managed with CKM were higher in the later years of the study period compared with the initial years, with interannual variability in both series. These patterns likely reflect multiple factors, including increasing life expectancy, broader eligibility for KRT, and advances in cardiovascular and CKD care; the integrated care program may also have contributed within this broader context. Comparative analyses across territories would help better assess population-level effects in future studies.
Diagnostic precision has also emerged as a key component of quality care. The use of laboratory-based diagnostic algorithms can help enhance accuracy in both directions, by identifying unrecorded cases and by avoiding unnecessary disease labeling. Although CKD diagnoses in the district have increased steadily over time, the current recorded prevalence (6.9%) remains below the estimated 10% in the general population. This difference likely reflects a combination of factors, including the fact that a small proportion of residents receive care through private providers not captured in CatSalut registries, structural limitations in territorial data aggregation and interoperability across care settings, and variability in diagnostic recording practices in routine care. This is particularly relevant for conditions like CKD, where a large proportion of diagnoses rely on laboratory values. In this context, some PC physicians may choose not to register CKD in very elderly patients who technically meet the diagnostic criteria due to a mildly reduced eGFR; however, this should be regarded as a plausible additional explanation rather than the sole reason for the observed gap, and it was not directly assessed through age-stratified analyses in the present study. This reflects the ongoing debate on whether current CKD definitions should incorporate age-adjusted thresholds for eGFR, an important but complex issue that lies beyond the scope of this article.15,16
Beyond diagnostic precision, the program has also highlighted the potential of nursing to further strengthen integration. In addition to dialysis and transplant nurses, the hospital runs specialized outpatient clinics in CKD and in hypertension and cardiovascular risk. These nurses are now positioned to lead virtual consultations with PC nurses, offering support in CKD and hypertension management and reinforcing coordination across settings.
International experiences show that integrated CKD care can be implemented through diverse models adapted to local context. In Canada, two recent studies from Alberta highlight key challenges and innovations in early-stage CKD care. The My Kidneys My Health study emphasizes the co-design of digital self-management strategies with patients and caregivers, aiming to support person-centered care in primary and nephrology settings.17 Complementing this, a cross-sectional survey assessing person-centered integrated care for individuals with mild to moderate CKD underscored the need for better care coordination, team-based approaches, and patient-centredness.18 In the United Kingdom, the LUCID project stands out for its integration of primary and secondary care through virtual multidisciplinary meetings and the use of risk stratification tools such as the Kidney Failure Risk Equation (KFRE), which estimates individual progression to end-stage kidney disease and supports referral prioritization and intervention planning.19 In Australia, Bonner et al. describe a nurse practitioner-led clinic managing CKD alongside other chronic conditions, demonstrating improvements in efficiency and patient satisfaction.20 At a broader level, Australian initiatives have also developed interoperable digital tools and cross-sector partnerships to strengthen coordination and assess cost-effectiveness, even in resource-limited settings.21,22 Finally, a recent Australian review highlights the need to redesign CKD care models, identifying major gaps in early detection, fragmented care, and limited access, particularly in disadvantaged populations. The authors propose integrated, nurse-led, pharmacy-led, and digital models to improve outcomes.23 Taken together, these international experiences demonstrate the versatility of integrated CKD care, from digital co-design and nurse-led clinics to risk-based stratification and cross-sector partnerships. Yet despite promising results, many initiatives remain limited in scope or duration, revealing the ongoing challenge of embedding integration into routine, system-wide practice.
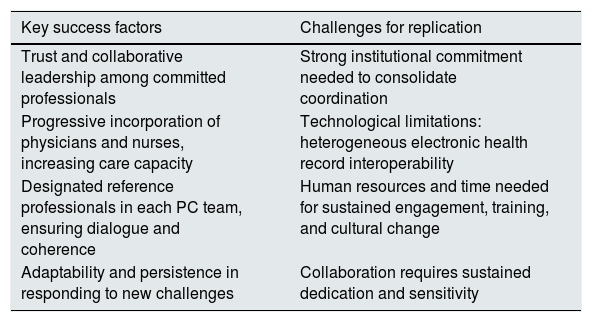
In contrast, the AP AIS Dreta-Fundació Puigvert Program exemplifies how long-term, territory-wide integration between PC and nephrology can be achieved and sustained. Its continuity for more than 25 years, together with systematic involvement of PC teams and the use of interoperable data tools, makes it a distinctive and mature model. The program is supported by balanced human resources across care levels, ensuring adequate staffing in both PC and nephrology to sustain integrated CKD management (Table 2). This experience shows that integrated CKD care is not only feasible but can become an established way of organizing services at the population level.
Key success factors and challenges for replicating the AIS Dreta CKD program.
| Key success factors | Challenges for replication |
|---|---|
| Trust and collaborative leadership among committed professionals | Strong institutional commitment needed to consolidate coordination |
| Progressive incorporation of physicians and nurses, increasing care capacity | Technological limitations: heterogeneous electronic health record interoperability |
| Designated reference professionals in each PC team, ensuring dialogue and coherence | Human resources and time needed for sustained engagement, training, and cultural change |
| Adaptability and persistence in responding to new challenges | Collaboration requires sustained dedication and sensitivity |
Several limitations should be acknowledged. Although the program covers the publicly funded healthcare network of the district, a small proportion of residents receive care from private providers, which are not captured in CatSalut registries. This may lead to an underestimation of the true CKD population and related care indicators. In addition, some challenges persist: LDL cholesterol control remains suboptimal, albuminuria is measured annually in only one-third of patients, and virtual nursing consultations are still limited. Fragmented data environments and limited interoperability between systems also constrain indicator retrieval and continuous monitoring. Addressing these limitations will require technical solutions, governance efforts, and sustained institutional support to standardize data flows and close persistent care gaps.
In conclusion, this 25-year experience demonstrates that sustained collaboration between PC and nephrology can be consolidated over time within a real-world territorial setting, supporting coordinated CKD detection, management, and follow-up. The AP AIS Dreta-Fundació Puigvert program combines shared care pathways, professional training, patient-centered initiatives, and continuous evaluation within a coordinated, data-driven framework. Its main strengths lie in organizational consolidation and continuity of care, while several clinical indicators still highlight relevant areas for improvement. Future priorities include reinforcing diagnostic quality, expanding nursing-led virtual care, and improving data interoperability across care settings. In addition, a robust cost-effectiveness evaluation is essential to demonstrate the program's value and secure its long-term sustainability. Ultimately, this experience suggests that integrated care is not a static model but a dynamic, evolving framework. With sustained institutional commitment and adequate resources, its core principles may be applied in other regions and to the management of chronic conditions beyond CKD, contributing to more sustainable and patient-centered health systems.
Declaration of generative AI and AI-assisted technologies in the writing processDuring the preparation of this work, the authors used generative artificial intelligence tools to support language editing and translation. After using these tools, the authors reviewed and edited the content as needed and take full responsibility for the content of the publication.
FundingThis work did not receive any specific funding.
Conflicts of interestThe authors declare that they have no conflicts of interest.
We sincerely thank the contribution of the following members of the CKD Integrated Care Working Group of AP AIS Dreta-Fundació Puigvert, who played an essential role in the development and implementation of the programme.
Nuria Aranda, EAP Guinardo-, Institut Català de la Salut, Barcelona, Spain.
Sílvia Benito, Nephrology Department, Fundació Puigvert, IR-SANT PAU, Universitat Autònoma de Barcelona, Barcelona, Spain.
Ignasi Bolivar, Servicio de Epidemiología Clínica y Salud Pública, Hospital de la Santa Creu i Sant Pau, Barcelona, España.
Elisabet Coll, Nephrology Department, Fundació Puigvert, IR-SANT PAU, Universitat Autònoma de Barcelona, Barcelona, Spain.
Joan Manel Diaz, Nephrology Department, Fundació Puigvert, IR-SANT PAU, Universitat Autònoma de Barcelona, Barcelona, Spain.
Tania Fernández, Hypertension and kidney damage prevention nurse, Department of Nursing, Fundació Puigvert, Barcelona, Spain.
Marisa Galán, EAP Sardenya, Barcelona, Spain.
Lluis Guirado, Nephrology Department, Fundació Puigvert, IR-SANT PAU, Universitat Autònoma de Barcelona, Barcelona, Spain.
Silvia Gracia, Laboratory Department, Fundació Puigvert, IR-SANT PAU, Universitat Autònoma de Barcelona, Barcelona, Spain.
Mar Jarque, EAP Sanllehy, Institut Català de la Salut, Barcelona, Spain.
Mª Lourdes Lasaosa, Case manager nurse, EAP Passeig St Joan, Institut Català de la Salut, Barcelona, Spain.
Jesús Liesa, EAP Sagrera, Institut Català de la Salut, Barcelona, Spain.
Vivian Liste, EAP Sagrada Familia, Consorci sanitari integral, Barcelona, Spain.
Mireia Marsà, EAP Joanic, Institut Català de la Salut, Barcelona, Spain.
Laia Mingo, Case manager nurse, Department of Nursing, Fundació Puigvert, Barcelona, Spain.
Marta Roset, EAP Congres, Institut Català de la Salut, Barcelona.
Laia Salinas, EAP Dreta Roger de Flor, Spain.
Esther Sanz, Izquierdo Chronic kidney disease nurse, Department of Nursing, Fundació Puigvert, Barcelona, Spain.
Pau Sendra, EAP Dreta Roger de Flor, Brcelona, Spain.
Darila Vinciguerra, EAP Vila de Gracia, Institut Català de la Salut, Barcelona, Spain.
We also thank Núria Viñolas and Lluïsa Ponsa for their invaluable administrative support throughout these years, which has greatly facilitated the coordination and continuity of the programme.




