




Rituximab is first-line therapy for moderate- and high-risk primary membranous nephropathy, yet approximately one-third of patients fail to achieve remission. Accelerated rituximab clearance through urinary loss drives interindividual pharmacokinetic variability; undetectable serum rituximab at month 3 independently predicts treatment failure. We hypothesised that serum rituximab measured on day 15—immediately before the second infusion—predicts composite clinical response at month 6.
MethodsIn this single-centre prospective cohort study, 46 adults with moderate- or high-risk pMN initiating rituximab-based therapy (monotherapy, n=22; combination with calcineurin inhibitor and glucocorticoid, n=24) underwent serum rituximab measurement on day 15 using the IDKmonitor ELISA. The primary endpoint was the association between day-15 rituximab level and composite clinical response (complete or partial remission) at month 6.
ResultsComposite clinical response at month 6 was achieved in 32 patients (69.6%). Day-15 rituximab was significantly higher in responders than non-responders (113.2±58.0 vs 48.6±55.0μg/mL; p=0.001). A threshold of 56μg/mL yielded response rates of 87.1% versus 33.3% (sensitivity 84.4%, specificity 71.4%). Despite significantly lower albumin and higher proteinuria, combination therapy patients achieved day-15 rituximab levels comparable to monotherapy (94.1±54.9 vs 92.9±74.0μg/mL; p=0.95).
ConclusionsDay-15 serum rituximab predicts month-6 clinical response in pMN, advancing the earliest predictive pharmacokinetic timepoint described in this disease. Combination therapy with a calcineurin inhibitor and low-dose corticosteroid was associated with preserved day-15 rituximab exposure despite more severe baseline disease, suggesting that early proteinuria reduction may help maintain drug bioavailability. If confirmed in multicentre cohorts, day-15 measurement could enable timely treatment individualisation before irreversible underexposure leads to disease progression.
El rituximab es un tratamiento de primera línea para la nefropatía membranosa primaria de riesgo moderado y alto; sin embargo, aproximadamente un tercio de los pacientes no logra alcanzar la remisión. La eliminación acelerada de rituximab mediante pérdida urinaria determina la variabilidad farmacocinética interindividual; la ausencia de rituximab sérico detectable en el mes 3 predice de manera independiente el fracaso terapéutico. Planteamos la hipótesis de que la concentración sérica de rituximab medida en el día 15—inmediatamente antes de la segunda infusión—predice la respuesta clínica compuesta en el mes 6.
MétodosEn este estudio prospectivo de cohorte realizado en un único centro, 46 adultos con nefropatía membranosa primaria de riesgo moderado o alto que iniciaron un tratamiento basado en rituximab (monoterapia, n=22; combinación con un inhibidor de la calcineurina y un glucocorticoide, n=24) fueron sometidos a la medición de rituximab sérico en el día 15 mediante el ensayo ELISA IDKmonitor. El criterio de valoración principal fue la asociación entre la concentración de rituximab en el día 15 y la respuesta clínica compuesta (remisión completa o parcial) en el mes 6.
ResultadosLa respuesta clínica compuesta en el mes 6 se alcanzó en 32 pacientes (69,6%). La concentración de rituximab en el día 15 fue significativamente mayor en los pacientes respondedores que en los no respondedores (113,2 ± 58 frente a 48,6 ± 55 μg/mL; p=0,001). Un valor umbral de 56 μg/mL se asoció con tasas de respuesta del 87,1% frente al 33,3% (sensibilidad del 84,4%, especificidad del 71,4%). A pesar de presentar concentraciones de albúmina significativamente menores y una proteinuria mayor, los pacientes tratados con la terapia combinada alcanzaron concentraciones de rituximab en el día 15 comparables a las observadas con la monoterapia (94,1 ± 54,9 frente a 92,9 ± 74,0 μg/mL; p=0,95).
ConclusionesLa concentración sérica de rituximab en el día 15 predice la respuesta clínica en el mes 6 en la nefropatía membranosa primaria, adelantando el punto temporal farmacocinético predictivo más precoz descrito en esta enfermedad. La terapia combinada con un inhibidor de la calcineurina y un corticosteroide a dosis bajas se asoció con la preservación de la exposición a rituximab en el día 15, a pesar de una enfermedad basal más grave, lo que sugiere que la reducción temprana de la proteinuria puede contribuir a mantener la biodisponibilidad del fármaco. Si estos hallazgos se confirman en cohortes multicéntricas, la medición en el día 15 podría permitir la individualización oportuna del tratamiento antes de que una infraexposición irreversible conduzca a la progresión de la enfermedad.

Primary membranous nephropathy (pMN) is the leading cause of nephrotic syndrome in non-diabetic adults.1 Rituximab (RTX) is now established as a first-line immunosuppressive therapy for patients at moderate or high risk of progressive disease.2 Approximately 30–40% of patients, however, fail to achieve remission.3 Interindividual variability in RTX pharmacokinetics, is a major contributor to treatment failure, driven largely by the degree of proteinuria4; hypoalbuminaemia, body weight, and anti-drug antibody formation are additional established covariates.5 The mean serum half-life of RTX in MN is approximately 11.5 days—roughly half that observed in non-proteinuric autoimmune conditions—and month-3 residual drug levels are dramatically lower than in patients without proteinuria.6 Urinary loss of intact RTX through the damaged glomerular filtration barrier has been identified as the principal mechanism of this accelerated clearance.7
Serum RTX concentration has accordingly been investigated as a predictor of treatment outcome. Teisseyre and colleagues reported that undetectable serum rituximab (<2μg/mL) at month 3 independently predicted failure to achieve remission in a 68-patient prospective cohort.8 However, a three-month delay in identifying treatment failure prolongs exposure to the thromboembolic, infectious, and metabolic complications of persistent nephrotic syndrome, and postpones any treatment modification. The predictive value of serum RTX at earlier timepoints in pMN has not been studied.
In this prospective cohort study, our primary objective was to determine whether serum rituximab measured on day 15, immediately before the second infusion, predicts composite clinical response (complete or partial remission) at month 6 in moderate- and high-risk pMN. Secondary objectives were to assess the association of day-15 levels with response at months 1 and 3, the relationship of day-105 levels and CD19+ B-cell depletion with month-6 response, and to compare rituximab exposure between monotherapy and combination (calcineurin inhibitor plus corticosteroid) regimens.
Materials and methodsStudy design and settingThis prospective cohort study was conducted between May 2024 and May 2025 at the Department of Nephrology, Gazi University Faculty of Medicine. The article is reported in concordance with STROBE guidelines.
ParticipantsAdult patients (aged 18–80 years) diagnosed with pMN and classified as moderate or high risk according to the KDIGO 2021 guideline who were initiated on RTX-based therapy were eligible for inclusion.2 Risk group definitions are provided in Supplementary Material. Exclusion criteria were rapidly progressive glomerulonephritis, secondary MN, anti-glomerular basement membrane disease or ANCA-associated vasculitis, refusal of RTX therapy, prior steroid and calcineurin inhibitor (CNI) use at the time of RTX initiation, and inability to provide informed consent.
Of 71 patients screened, 25 were excluded at final analysis, yielding a final cohort of 46 patients. Flowchart of patient selection is presented in Fig. 1.
Treatment
Therapeutic regimens were selected in accordance with KDIGO 2021 recommendations, based on clinical status and physician discretion. Twenty-two patients received RTX monotherapy at 1000mg on days 0 and 15. The remaining 24 were treated with our department's combination regimen. In this regimen, rituximab, the CNI, and the corticosteroid were initiated concurrently; patients already receiving a CNI, with or without a corticosteroid, at the time of rituximab initiation were excluded (Fig. 1) to avoid confounding by prior immunosuppressive exposure.
This regimen adds RTX to the original cyclosporine–corticosteroid protocol of Cattran et al.,9 incorporating two key modifications. First, the prednisolone schedule was simplified: 15mg/day for one month, 10mg/day for one month, 5mg/day for one month, then stopped. Second, tacrolimus was introduced as an alternative CNI. Cyclosporine was dosed at 3.0–3.5mg/kg/day and tacrolimus at 0.05mg/kg/day; trough concentrations (125–225ng/mL and 5–10ng/mL, respectively) were used as reference thresholds, with dose adjustments reserved for cases of toxicity or inadequate response. Responders continued the CNI for three months before tapering and discontinuation; non-responders maintained it for up to 12 months.
Variables and measurementsBaseline demographic data, comorbidities, concomitant medications, serum creatinine, estimated glomerular filtration rate (CKD-EPI 2021), serum albumin, lipid profile, proteinuria, and anti-phospholipase A2 receptor (PLA2R) antibody levels were extracted from the electronic health records. Serum RTX concentrations were measured at two timepoints: day 15 (immediately before the second infusion) and month 3 (day 105 from the first infusion). Samples were analysed using the IDKmonitor Rituximab Drug Level ELISA (Immundiagnostik AG, Bensheim, Germany), with a lower detection limit of 5.08μg/mL and an inter-assay coefficient of variation<10%.
CD19+ B-cell counts were determined by flow cytometry using CD45-Krome Orange and CD19-ECD antibodies (Beckman Coulter). Complete B-cell depletion was defined as CD19+ cells ≤1% of total lymphocytes.
Anti-PLA2R antibodies were measured using the EUROIMMUN anti-PLA2R ELISA (EUROIMMUN AG, Lübeck, Germany). Results were classified as negative (<14RU/mL), borderline (14–19RU/mL), or positive (≥20RU/mL).
OutcomesThe primary endpoint was the association between day-15 serum rituximab level and composite clinical response at month 6. Clinical response was defined according to KDIGO 2012 criteria as either complete remission (proteinuria<0.3g/day on at least two consecutive measurements, with serum albumin normalisation and stable kidney function) or partial remission (proteinuria<3.5g/day with at least 50% reduction from baseline, accompanied by improvement in serum albumin and stable kidney function).10 Complete and partial remission were analysed as a composite endpoint because of the limited sample size.
Secondary endpoints included the association of day-15 RTX levels with clinical response at months 1 and 3, the association of day-105 rituximab levels with month-6 response, the relationship between CD19+ B-cell depletion and month-6 response, and the comparison of RTX levels between the monotherapy and combination therapy groups.
Statistical analysisContinuous variables were tested for normality using the Shapiro–Wilk test and expressed as mean±standard deviation or median (interquartile range) as appropriate. Serum RTX concentrations are reported as mean±SD. Group comparisons were performed using the independent-samples t-test or Mann–Whitney U test for continuous variables and the Chi-square test or Fisher's exact test for categorical variables.
To determine a clinically informative threshold for day-15 rituximab levels, concentrations were first divided into tertiles. A linear-by-linear association test confirmed a significant trend between increasing tertile category and clinical response rate. Based on this trend, levels were dichotomized at the lower tertile boundary (56μg/mL). Diagnostic performance of this threshold for predicting composite clinical response was assessed by calculating sensitivity, specificity, positive predictive value, and negative predictive value from the resulting 2×2 contingency table. Given the limited event count (14 non-responders), threshold selection was treated as exploratory. Stability of the 56μg/mL threshold was assessed by bootstrap resampling (2500 resamples; seed 20260707), examining both the distribution of the data-derived optimal cut-point and the diagnostic performance at the fixed threshold. The continuous association between day-15 rituximab and clinical response was quantified by univariable logistic regression, expressed as the odds ratio per 10μg/mL increment, with discrimination summarised by the area under the receiver operating characteristic curve and internal optimism estimated by bootstrap. Multivariable modelling was not undertaken given the sample size and event count. As the primary analysis rested on a single dichotomised comparison, no adjustment for multiple comparisons was applied; associations at months 1 and 3 are presented as supportive secondary analyses. All analyses were performed using IBM SPSS Statistics version 22.0 (IBM Corp., Armonk, NY, USA). A two-sided p value<0.05 was considered statistically significant.
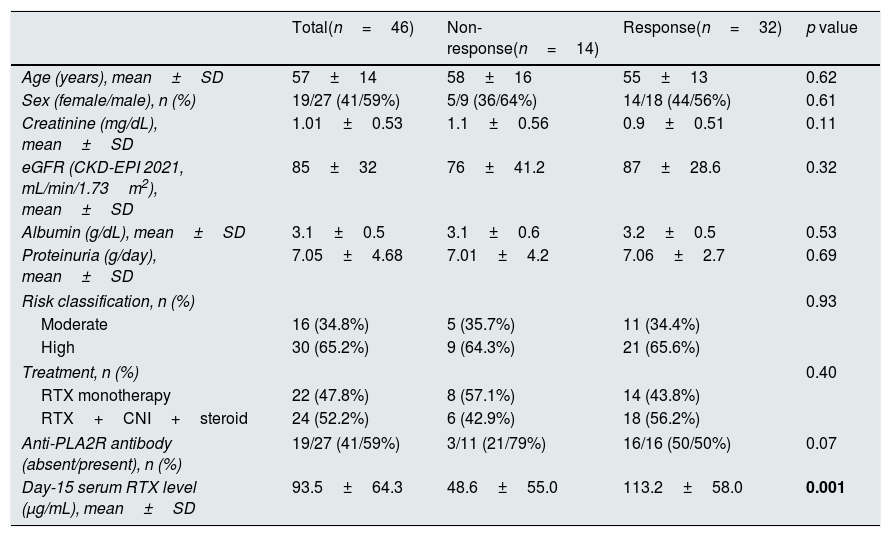
ResultsStudy populationOf 71 patients screened, 25 were excluded (Fig. 1), yielding a final cohort of 46 patients. Baseline age, sex, eGFR, proteinuria, serum albumin, anti-PLA2R positivity, and KDIGO risk classification were comparable between the 25 excluded patients and the final cohort (Supplementary Table 1). The mean age was 57±14 years, 27 (59%) were male, and 30 (65.2%) were classified as high risk. The baseline demographic and clinical characteristics of the entire cohort, stratified by treatment response at month 6, are presented in Table 1. No statistically significant differences were observed between responders and non-responders in age, sex, kidney function, serum albumin, proteinuria, risk classification, or treatment regimen (all p>0.05). Anti-PLA2R antibody positivity was numerically more frequent among non-responders (79% vs 50%), though this difference did not reach statistical significance (p=0.07). Day-15 serum RTX level was the only measured variable that differed significantly between groups (113.2±58.0 vs 48.6±55.0μg/mL; p=0.001).
Baseline clinical and laboratory characteristics of the study cohort, stratified by treatment response at month 6.
| Total(n=46) | Non-response(n=14) | Response(n=32) | p value | |
|---|---|---|---|---|
| Age (years), mean±SD | 57±14 | 58±16 | 55±13 | 0.62 |
| Sex (female/male), n (%) | 19/27 (41/59%) | 5/9 (36/64%) | 14/18 (44/56%) | 0.61 |
| Creatinine (mg/dL), mean±SD | 1.01±0.53 | 1.1±0.56 | 0.9±0.51 | 0.11 |
| eGFR (CKD-EPI 2021, mL/min/1.73m2), mean±SD | 85±32 | 76±41.2 | 87±28.6 | 0.32 |
| Albumin (g/dL), mean±SD | 3.1±0.5 | 3.1±0.6 | 3.2±0.5 | 0.53 |
| Proteinuria (g/day), mean±SD | 7.05±4.68 | 7.01±4.2 | 7.06±2.7 | 0.69 |
| Risk classification, n (%) | 0.93 | |||
| Moderate | 16 (34.8%) | 5 (35.7%) | 11 (34.4%) | |
| High | 30 (65.2%) | 9 (64.3%) | 21 (65.6%) | |
| Treatment, n (%) | 0.40 | |||
| RTX monotherapy | 22 (47.8%) | 8 (57.1%) | 14 (43.8%) | |
| RTX+CNI+steroid | 24 (52.2%) | 6 (42.9%) | 18 (56.2%) | |
| Anti-PLA2R antibody (absent/present), n (%) | 19/27 (41/59%) | 3/11 (21/79%) | 16/16 (50/50%) | 0.07 |
| Day-15 serum RTX level (μg/mL), mean±SD | 93.5±64.3 | 48.6±55.0 | 113.2±58.0 | 0.001 |
CKD-EPI: Chronic Kidney Disease Epidemiology Collaboration; CNI: calcineurin inhibitor; eGFR: estimated glomerular filtration rate; PLA2R: phospholipase A2 receptor; RTX: rituximab; SD: standard deviation. Bold p values indicate statistical significance (p<0.05). Day-15 serum rituximab was the only variable significantly associated with month-6 clinical response.
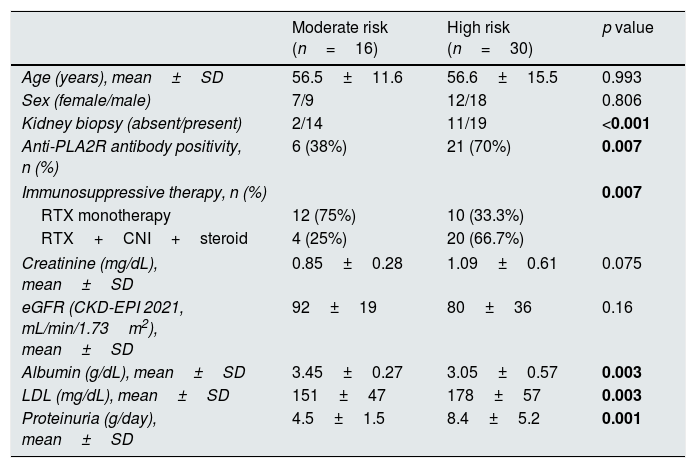
Kidney function was similar between moderate- and high-risk groups; however, serum albumin was significantly lower (3.05±0.57 vs 3.45±0.27g/dL; p=0.003), LDL cholesterol higher (178±57 vs 151±47mg/dL; p=0.003), and proteinuria more severe (8.4±5.2 vs 4.5±1.5g/day; p=0.001) in the high-risk group. The proportion of patients receiving combination therapy was significantly greater in the high-risk group (66.7% vs 25%; p=0.007) (Table 2).
Baseline clinical and laboratory characteristics by risk classification.
| Moderate risk (n=16) | High risk (n=30) | p value | |
|---|---|---|---|
| Age (years), mean±SD | 56.5±11.6 | 56.6±15.5 | 0.993 |
| Sex (female/male) | 7/9 | 12/18 | 0.806 |
| Kidney biopsy (absent/present) | 2/14 | 11/19 | <0.001 |
| Anti-PLA2R antibody positivity, n (%) | 6 (38%) | 21 (70%) | 0.007 |
| Immunosuppressive therapy, n (%) | 0.007 | ||
| RTX monotherapy | 12 (75%) | 10 (33.3%) | |
| RTX+CNI+steroid | 4 (25%) | 20 (66.7%) | |
| Creatinine (mg/dL), mean±SD | 0.85±0.28 | 1.09±0.61 | 0.075 |
| eGFR (CKD-EPI 2021, mL/min/1.73m2), mean±SD | 92±19 | 80±36 | 0.16 |
| Albumin (g/dL), mean±SD | 3.45±0.27 | 3.05±0.57 | 0.003 |
| LDL (mg/dL), mean±SD | 151±47 | 178±57 | 0.003 |
| Proteinuria (g/day), mean±SD | 4.5±1.5 | 8.4±5.2 | 0.001 |
CKD-EPI: Chronic Kidney Disease Epidemiology Collaboration; CNI: calcineurin inhibitor; eGFR: estimated glomerular filtration rate; LDL: low-density lipoprotein; PLA2R: phospholipase A2 receptor; RTX: rituximab; SD: standard deviation. Bold p values indicate statistical significance (p<0.05).
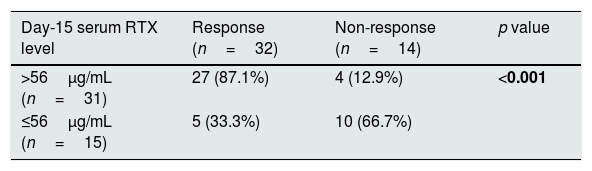
At month 6, 32 patients (69.6%) achieved composite clinical response (16 complete and 16 partial remission) and 14 (30.4%) were non-responders. When day-15 RTX levels were divided into tertiles, a significant linear trend was observed between increasing tertile category and clinical response rate (linear-by-linear association, p<0.001). Based on this trend, levels were dichotomized at the lower tertile boundary (56μg/mL). Among 31 patients with day-15 RTX>56μg/mL, 27 (87.1%) achieved clinical response at month 6, compared with 5 of 15 (33.3%) patients with levels ≤56μg/mL (p<0.001). Using >56μg/mL as a predictor of composite response, sensitivity was 84.4%, specificity 71.4%, positive predictive value 87.1%, and negative predictive value 66.7% (Table 3).
Association between day-15 serum rituximab level and clinical response at month 6.
| Day-15 serum RTX level | Response (n=32) | Non-response (n=14) | p value |
|---|---|---|---|
| >56μg/mL (n=31) | 27 (87.1%) | 4 (12.9%) | <0.001 |
| ≤56μg/mL (n=15) | 5 (33.3%) | 10 (66.7%) |
| Sensitivity | Specificity | PPV | NPV |
|---|---|---|---|
| 84.4% | 71.4% | 87.1% | 66.7% |
NPV: negative predictive value; PPV: positive predictive value; RTX: rituximab. The 56μg/mL threshold was derived from the lower tertile boundary of the day-15 rituximab distribution. Bold p value indicates statistical significance (p<0.05).
The predictive value of day-15 levels was consistent across earlier timepoints; similar associations were observed at months 1 (p<0.001) and 3 (p=0.004), (Fig. 2, Supplementary Table 2).

Across 2500 bootstrap resamples, the data-derived optimal cut-point clustered around the pre-specified threshold (lower-tertile median 58.4μg/mL, interquartile range 45.0–64.5; Youden median 52.6μg/mL), with approximately 70% of resamples falling within 40–70μg/mL, and three independent derivation rules converged (lower tertile 58.4, Youden 52.6, pre-specified 56μg/mL). Diagnostic performance at 56μg/mL was preserved across resamples (sensitivity 84.8% [interquartile range 80.0–88.9], specificity 72.2% [63.6–80.0], positive predictive value 87.5% [83.3–91.4], negative predictive value 66.7% [58.3–75.0]). On the continuous scale, each 10μg/mL increment in day-15 rituximab was associated with higher odds of month-6 response (odds ratio 1.27, 95% CI 1.07–1.50; p=0.005), with an area under the curve of 0.824 and an optimism-corrected area under the curve of 0.821.
The association between day-15 rituximab category and month-6 response was consistent across clinical strata: response rates for day-15>56 versus ≤56μg/mL were 83% versus 25% in the moderate-risk group and 89% versus 36% in the high-risk group, and 92% versus 22% in the monotherapy group and 83% versus 50% in the combination group (Supplementary Table 3).
Among responders, all 16 complete remissions occurred in patients with day-15 rituximab>56μg/mL (16 complete, 11 partial), whereas all 5 responders with day-15 ≤56μg/mL achieved partial remission only. The composite endpoint was pre-specified for the primary analysis given the event count, with this distribution provided as an exploratory observation.
Day-105 serum RTX levelAt day 105, RTX was undetectable (0μg/mL) in 19 patients (41.3%) and detectable in 27 (58.7%). Among patients with undetectable day-105 levels, 8 (42.1%) achieved clinical response at month 6, compared with 24 of 27 (88.9%) with detectable levels (p=0.001) (Supplementary Table 4).
CD19+ B-cell depletionCD19+ B-cell depletion was achieved in 44 of 46 patients (95.6%) at day 15 and in all patients by day 105. All 32 responders demonstrated CD19+ B-cell depletion at day 15, whereas depletion was absent in 2 of 14 non-responders (14.3%). This difference did not reach statistical significance (p=0.088) (Supplementary Table 5).
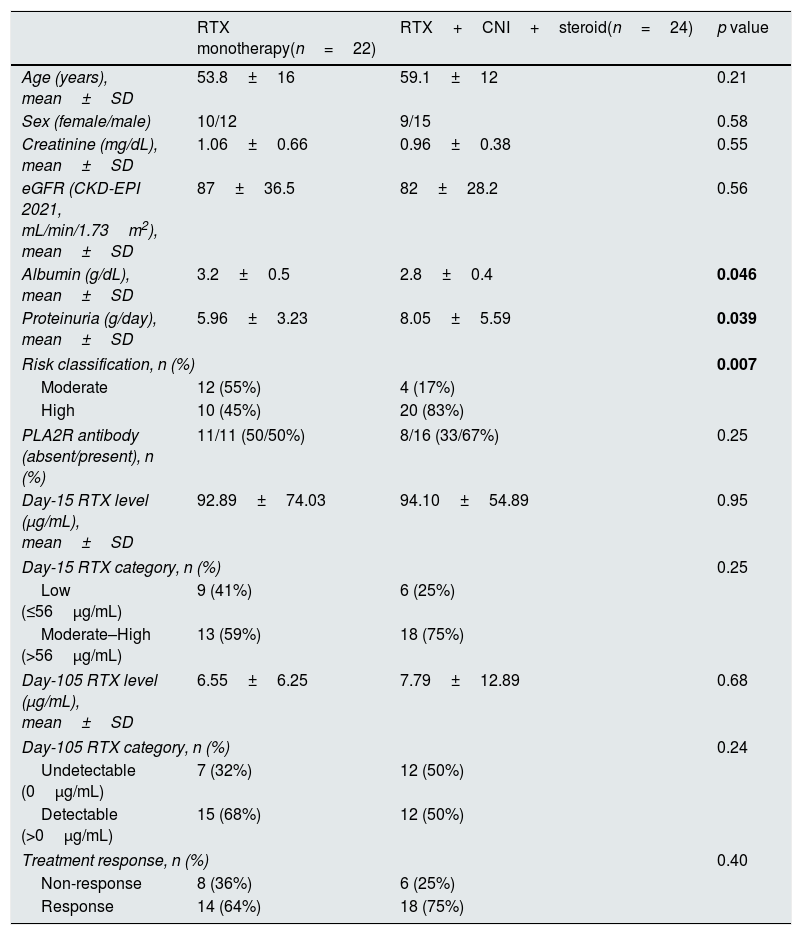
Serum RTX levels by treatment groupTwenty-two patients received RTX monotherapy and 24 received RTX combined with a CNI and glucocorticoid. Patients in the combination group had significantly lower albumin (2.8±0.4 vs 3.2±0.5g/dL; p=0.046), higher proteinuria (8.05±5.59 vs 5.96±3.23g/day; p=0.039), and a greater proportion of high-risk classification (83% vs 45%; p=0.007). Despite this more severe disease profile, day-15 serum RTX levels were comparable between groups (94.10±54.89 vs 92.89±74.03μg/mL; p=0.95). Day-105 levels were also similar (7.79±12.89 vs 6.55±6.25μg/mL; p=0.68) (Table 4).
Comparison of clinical and laboratory characteristics across treatment groups.
| RTX monotherapy(n=22) | RTX+CNI+steroid(n=24) | p value | |
|---|---|---|---|
| Age (years), mean±SD | 53.8±16 | 59.1±12 | 0.21 |
| Sex (female/male) | 10/12 | 9/15 | 0.58 |
| Creatinine (mg/dL), mean±SD | 1.06±0.66 | 0.96±0.38 | 0.55 |
| eGFR (CKD-EPI 2021, mL/min/1.73m2), mean±SD | 87±36.5 | 82±28.2 | 0.56 |
| Albumin (g/dL), mean±SD | 3.2±0.5 | 2.8±0.4 | 0.046 |
| Proteinuria (g/day), mean±SD | 5.96±3.23 | 8.05±5.59 | 0.039 |
| Risk classification, n (%) | 0.007 | ||
| Moderate | 12 (55%) | 4 (17%) | |
| High | 10 (45%) | 20 (83%) | |
| PLA2R antibody (absent/present), n (%) | 11/11 (50/50%) | 8/16 (33/67%) | 0.25 |
| Day-15 RTX level (μg/mL), mean±SD | 92.89±74.03 | 94.10±54.89 | 0.95 |
| Day-15 RTX category, n (%) | 0.25 | ||
| Low (≤56μg/mL) | 9 (41%) | 6 (25%) | |
| Moderate–High (>56μg/mL) | 13 (59%) | 18 (75%) | |
| Day-105 RTX level (μg/mL), mean±SD | 6.55±6.25 | 7.79±12.89 | 0.68 |
| Day-105 RTX category, n (%) | 0.24 | ||
| Undetectable (0μg/mL) | 7 (32%) | 12 (50%) | |
| Detectable (>0μg/mL) | 15 (68%) | 12 (50%) | |
| Treatment response, n (%) | 0.40 | ||
| Non-response | 8 (36%) | 6 (25%) | |
| Response | 14 (64%) | 18 (75%) | |
CKD-EPI: Chronic Kidney Disease Epidemiology Collaboration; CNI: calcineurin inhibitor; eGFR: estimated glomerular filtration rate; PLA2R: phospholipase A2 receptor; RTX: rituximab; SD: standard deviation. Bold p values indicate statistical significance (p<0.05).
No deaths occurred in the final cohort during the 6-month follow-up. In the monotherapy group (n=22), infections were recorded in 3 patients and hospitalisation in 2, with no new-onset diabetes; in the combination group (n=24), infections occurred in 4 patients (5 episodes), hospitalisation in 1, and new-onset diabetes in 3.
DiscussionWe hypothesised that serum rituximab measured on day 15, immediately before the second infusion, predicts composite clinical response at month 6 in moderate- and high-risk pMN—a hypothesis this study supports. Building on the observation that undetectable month-3 serum RTX independently predicts treatment failure, we advance this monitoring window by approximately 10 weeks—to our knowledge the earliest timepoint at which serum RTX has been shown to carry prognostic value in pMN.8
Bootstrap resampling supported the 56μg/mL operating threshold: independent derivation rules converged on 52–58μg/mL, and diagnostic performance at 56μg/mL was maintained across resamples, while the continuous exposure–response relationship was strong and internally validated (optimism-corrected area under the curve 0.82). Defining the precise decision limit within the 50–60μg/mL range, and confirming its transferability across assay platforms, is the task of larger externally validated cohorts using standardised assays; our data indicate that a clinically actionable pharmacokinetic signal is measurable as early as day 15.
The biological plausibility of day 15 as a predictive timepoint is supported by the pharmacokinetic profile of RTX in pMN. Fogueri et al. reported a mean serum half-life of approximately 11.5 days—roughly half that observed in non-proteinuric conditions.6 Larrosa-García and colleagues confirmed a similar half-life and identified proteinuria>2.4g/day as a threshold for significantly accelerated clearance,11 while Boyer-Suavet and colleagues provided direct clinical evidence that month-3 residual RTX levels in pMN are approximately sixfold lower than in non-proteinuric patients receiving an identical regimen.12 Day 15 therefore corresponds to approximately one elimination half-life after the first infusion, making it a physiologically rational timepoint at which underexposure first becomes detectable.
The mechanism driving this underexposure was rigorously characterised by Allinovi and colleagues in a prospective Florentine cohort, who demonstrated that urinary loss of intact RTX through non-selective proteinuria directly reduces serum peak levels and predicts treatment failure—a commendable methodological contribution that nonetheless requires laboratory expertise not readily available outside specialist centres.7 Broader implementation of RTX monitoring faces additional practical barriers: LISA-TRACKER, employed by both Teisseyre8 and Destere,13 requires dedicated automated instrumentation and carries higher per-test costs.14 Inter-assay variability compounds this—Truffot and colleagues showed that the Promonitor kit underestimates RTX concentrations by a mean of 69% relative to LC-MS/MS, whereas LISA-TRACKER shows only 4% bias.15 The IDKmonitor kit employed in the present study has not been evaluated in such head-to-head analyses, and our 56μg/mL threshold may not be directly transferable across platforms. Nevertheless, measuring serum RTX at day 15 with a widely available ELISA on a conventional microplate reader represents a pragmatic alternative that could extend pharmacokinetic monitoring beyond the handful of centres currently equipped for it.
Despite more severe disease at baseline—lower albumin, higher proteinuria, and a greater proportion of high-risk classification—patients receiving combination therapy achieved day-15 and day-105 rituximab concentrations comparable to those on monotherapy. This was unexpected, as hypoalbuminaemia and heavy proteinuria are established drivers of accelerated RTX clearance.6,16 A pharmacokinetically plausible explanation is that CNI-mediated podocyte stabilisation17 may attenuate urinary rituximab loss and thereby help preserve systemic exposure, although causal inference is not possible in this observational dataset. This would be consistent with the striking remission rates reported by Waldman and colleagues with concurrent RTX and cyclosporine—92% CR+PR at 9 months18—and with subsequent data showing that CNI addition to RTX in refractory disease improves outcomes.19,20 To our knowledge, no prior study has directly compared serum RTX levels between monotherapy and combination therapy in pMN; this finding is hypothesis-generating and requires confirmation in a prospective, adequately powered cohort.
It should be noted that proteinuria is not the sole determinant of rituximab pharmacokinetics. In addition to several measurable clinical factors, urinary rituximab loss has been documented even in patients with selective proteinuria, and FcRn polymorphisms represent a further source of inter-individual variability.7,8,12 Hartinger and colleagues, through population pharmacokinetic modelling, identified body weight, serum albumin, disease type, treatment duration, and anti-drug antibody formation as independent covariates of rituximab exposure, and argued that dosing strategies should differ across glomerular diseases including FSGS, SLE, and MN.5 In the present cohort, the major measurable clinical determinants of rituximab clearance were largely comparable between responders and non-responders, yet day-15 serum RTX concentrations differed substantially—further supporting the value of direct pharmacokinetic measurement over any single clinical surrogate.
Established prediction models in pMN rely on parameters assessed at month 3 or later. Beck et al. showed that anti-PLA2R antibody kinetics precede clinical remission by months.21 In a prospective cohort of 132 patients, Ruggenenti and colleagues showed that a 50% fall in anti-PLA2R antibody levels preceded an equivalent reduction in proteinuria by approximately 10 months.22 A secondary analysis of the MENTOR trial reported a C-statistic of 0.93 when combining 3-month anti-PLA2R and albumin changes.23 Day-15 RTX measurement may offer a prognostic signal at a timepoint when none of these parameters have yet had time to evolve—though validation in larger cohorts is needed before firm conclusions can be drawn.
Our day-105 data are consistent with previously published month-3 findings. Detectable RTX at day 105 was associated with significantly higher response rates compared with undetectable levels (Supplementary Table 4), consistent with earlier month-3 immunomonitoring findings.8 Day-15 measurement, however, provides a prognostic signal at a timepoint when therapeutic intervention remains most feasible.
CD19+ B-cell depletion was achieved in 95.6% of patients at day 15 but did not predict clinical response (Supplementary Table 5), consistent with the GEMRITUX trial,24 a retrospective cohort evaluating B-cell depletion thresholds in MN,25 and a prospective study of post-RTX CD19 kinetics demonstrating that depletion was near-universal within weeks regardless of subsequent clinical outcome.26 Peripheral CD19 depletion reflects circulating B-cell elimination but does not capture tissue-resident B cells, long-lived plasma cells, or other effector mechanisms relevant to pMN pathogenesis.27 KDIGO 2021 does not endorse CD19 as a primary monitoring tool, reserving it as one factor in the evaluation of treatment failure.2
We propose a hypothetical, stepwise algorithm for the management of day-15 underexposure, summarised in Fig. 3 and outlined below. A day-15 RTX level below the exploratory threshold identifies insufficient drug exposure at a timepoint when therapeutic modification remains feasible. Additional RTX dosing may suffice in patients whose low levels reflect urinary loss—an approach supported by Allinovi and colleagues, in whom re-treatment of underexposed non-responders yielded clinical response in five of eight patients.7 CNI addition could simultaneously reduce proteinuria and preserve drug exposure, as our combination group data suggest and as the high remission rates with concurrent RTX-cyclosporine reported by Waldman and colleagues support.18 For patients in whom anti-drug immunity rather than urinary loss underlies treatment failure, agent substitution is preferable to dose escalation. Obinutuzumab has demonstrated markedly higher response rates than rituximab in refractory pMN,28–30 and its humanised structure may additionally overcome pre-existing anti-RTX immunity, which accumulates progressively with repeated courses.29,31–33 Obinutuzumab was not evaluated in the present study; the cited data support this management rationale rather than representing outcomes of our cohort. Because anti-drug antibodies were not measured, this algorithm cannot yet distinguish urinary loss from immunogenicity as the mechanism underlying day-15 underexposure. Accordingly, it cannot be used to infer the cause of underexposure in individual non-responders. Clinical implementation would require external validation in independent cohorts, together with cross-platform assay comparison. At present, the data support risk stratification only and do not justify protocolised dose adjustments.

This study has several limitations. No formal a priori sample-size or power calculation was performed; this is an exploratory single-centre cohort of 46 patients with 14 non-responders, which constrains multivariable modelling and external validation of the 56μg/mL threshold, derived from tertile distribution and regarded as exploratory, and residual confounding cannot be excluded. RTX was measured at only two timepoints (days 15 and 105), leaving intermediate kinetics undefined; tacrolimus and cyclosporine were not analysed separately, and the IDKmonitor ELISA has not been evaluated against LISA-TRACKER or LC-MS/MS, so the threshold may not transfer directly across platforms. Anti-drug antibodies were not measured, although 31 of 46 patients (67%) were rituximab-naïve, in whom pre-existing anti-rituximab antibodies would not be expected. Nevertheless, de novo anti-drug antibodies may have developed during follow-up, but this was not characterised in the present cohort. Complete and partial remission were analysed as a composite endpoint owing to limited event count, and follow-up was limited to 6 months, leaving the predictive value of day-15 levels for longer-term outcomes unknown.
ConclusionsIn conclusion, day-15 serum RTX concentration predicts clinical response at month 6 in moderate- and high-risk pMN, offering the earliest pharmacokinetic signal yet described in this disease. The 56μg/mL threshold identified in this study should be considered an exploratory operating value for hypothesis generation and internal risk stratification. It should not be interpreted as a decision threshold ready for clinical application. If confirmed in multicentre cohorts, this measurement could enable a precision medicine approach to pMN, individualising treatment intensity from the outset rather than correcting course only after failure.
Ethical disclosuresThe study was approved by the Ankara Etlik City Hospital Ethics Committee (Decision No: AEŞH-EK1-2024-0050, May 5, 2024) and conducted in accordance with the Declaration of Helsinki. Written informed consent was obtained from all participants.
Declaration of generative AI and AI-assisted technologies in the manuscript preparation processDuring the preparation of this work, the authors used Claude (Anthropic) to assist with language editing and figure preparation. The authors reviewed and edited the content as needed and take full responsibility for the content of the publication.
FundingThis work was supported by the Gazi University Scientific Research Projects Coordination Unit (BAP) [project code TTU-2025-9663].
Conflicts of interestAuthors declare no conflicts of interest.
Data availability statementData are available upon reasonable request from the corresponding author.
The followings are the supplementary data tot his article:





