



Fluid status assessment in patients undergoing hemodialysis (HD) remains a major clinical challenge, as no single reference method is currently available. Different tools, such as bioelectrical impedance spectroscopy (BIS), point-of-care ultrasound (PoCUS), and clinical assessment, explore distinct pathophysiological domains. The aim of this study was to evaluate the complementary role of different bedside tools assessing volume overload and hemodynamic congestion in HD patients.
Materials and methodsThis was a cross-sectional pilot study including 15 prevalent HD patients. A multiparametric pre-dialysis assessment was performed using BIS, PoCUS (lung ultrasound B-lines, inferior vena cava, and portal vein Doppler), and clinical evaluation. Congestion biomarkers, N-terminal pro-B-type natriuretic peptide (NT-proBNP) and carbohydrate antigen 125 (CA-125), were also analyzed. Exploratory descriptive agreement analyses using the weighted kappa coefficient, together with correlation analyses, were performed.
ResultsBIS identified volume overload in 80% of patients, compared to 26.7% by clinical assessment and 13.3% by PoCUS. Exploratory agreement analyses showed moderate concordance between clinical assessment and PoCUS (κ=0.59), low concordance between clinical assessment and BIS (κ=0.19), and very low concordance between BIS and PoCUS (κ=0.06). PoCUS identified a subgroup of patients with ultrasound findings suggestive of hemodynamic congestion, all corresponding to mild congestion. NT-proBNP levels were associated with both clinical congestion and BIS-estimated volume overload (rho≈0.67; p=0.007), while CA-125 showed a positive correlation with volume overload (rho≈0.58; p=0.025).
ConclusionsDifferent bedside tools identified divergent but complementary patterns of extracellular volume overload and hemodynamic congestion in HD patients. BIS, PoCUS, and clinical assessment should not be interpreted as equivalent or interchangeable tools, but rather as complementary methods exploring distinct physiological and hemodynamic domains. These exploratory findings support a multiparametric approach to fluid status evaluation and require confirmation in larger studies.
La evaluación del estado de hidratación en pacientes sometidos a hemodiálisis (HD) continúa siendo un importante desafío clínico, ya que actualmente no existe un único método de referencia disponible. Diferentes herramientas, como la espectroscopia de bioimpedancia eléctrica (BIS), la ecografía clínica a pie de cama (PoCUS) y la evaluación clínica, exploran distintos dominios fisiopatológicos. El objetivo de este estudio fue evaluar el papel complementario de diferentes herramientas a pie de cama para la valoración de la sobrecarga de volumen y la congestión hemodinámica en pacientes en HD.
Material y métodosSe realizó un estudio piloto transversal que incluyó 15 pacientes prevalentes en HD. Se llevó a cabo una evaluación multiparamétrica prediálisis mediante BIS, PoCUS (líneas B en ecografía pulmonar, vena cava inferior y Doppler de vena porta) y evaluación clínica. También se analizaron biomarcadores de congestión, incluyendo el péptido natriurético tipo B N-terminal (NT-proBNP) y el antígeno carbohidrato 125 (CA-125). Se realizaron análisis exploratorios de concordancia mediante el coeficiente kappa ponderado y análisis de correlación.
ResultadosLa BIS identificó sobrecarga de volumen en el 80% de los pacientes, en comparación con el 26,7% mediante evaluación clínica y el 13,3% mediante PoCUS. La concordancia fue moderada entre la evaluación clínica y PoCUS (κ=0,59), baja entre la evaluación clínica y BIS (κ=0,19) y muy baja entre BIS y PoCUS (κ=0,06). PoCUS identificó un subgrupo de pacientes con hallazgos ecográficos sugestivos de congestión hemodinámica, todos correspondientes a congestión leve. Los niveles de NT-proBNP se asociaron tanto con la congestión clínica como con la sobrecarga de volumen estimada por BIS (rho≈0,67; p=0,007), mientras que el CA-125 mostró una correlación positiva con la sobrecarga de volumen (rho≈0,58; p=0,025).
ConclusionesLas diferentes herramientas de evaluación a pie de cama identificaron patrones divergentes pero complementarios de sobrecarga de volumen extracelular y congestión hemodinámica en pacientes en HD. BIS, PoCUS y la evaluación clínica proporcionaron información no intercambiable que refleja dominios fisiológicos distintos, apoyando un enfoque multiparamétrico para la evaluación del estado de hidratación en la práctica clínica.
Assessment of fluid status remains one of the main challenges in patients undergoing hemodialysis (HD), as both volume overload and excessive ultrafiltration are associated with increased morbidity and mortality.1,2 However, the assessment of fluid status is complex, and currently there is no single reference method that allows accurate evaluation in routine clinical practice.1–3
It is important to recognize that the different tools used to assess fluid status explore distinct pathophysiological domains.2–5 Bioelectrical impedance spectroscopy (BIS) provides an estimation of extracellular volume, whereas point-of-care ultrasound (PoCUS) primarily identifies ultrasound findings associated with elevated filling pressures and venous congestion. Clinical evaluation, including the concept of dry weight, represents a dynamic construct that is symptom-dependent and has limited sensitivity for detecting early abnormalities.2–8
As a result, discrepancies between these methods are frequently observed in clinical practice.2,4 Rather than reflecting measurement error, such discordance may represent the complex and multidimensional relationship between volume overload and congestion in HD patients, particularly in the presence of cardiovascular comorbidity, diastolic dysfunction, or altered ventricular compliance.2,5
In this context, the concept of congestion has gained increasing relevance, not only as a manifestation of extracellular volume overload but also as a consequence of elevated cardiac filling pressures and systemic venous congestion. These hemodynamic alterations may impair organ perfusion and contribute to adverse cardiorenal interactions, even in the absence of overt clinical symptoms.6–8 In HD patients, cardiovascular remodeling, diastolic dysfunction, and altered ventricular compliance may further dissociate extracellular volume expansion from clinically apparent congestion.2,5 Consequently, PoCUS may provide clinically relevant information beyond simple volume estimation by identifying ultrasound findings associated with elevated filling pressures and systemic venous abnormalities.6–8 Identifying these patterns may have important implications for the individualization of ultrafiltration strategies in HD patients. However, the relationship between volume-derived parameters and indicators of hemodynamic congestion remains incompletely understood in this population.
Despite the growing interest in multiparametric approaches,2,4 few studies have comprehensively evaluated the relationship and potential complementarity between the different tools available for assessing fluid status and congestion in this setting.
Therefore, the primary objective of this pilot study was to explore the concordance and discordance between clinical assessment, BIS-derived extracellular volume estimation, and PoCUS-derived hemodynamic congestion parameters in HD patients, recognizing that these tools assess distinct but potentially complementary pathophysiological domains. Secondary exploratory objectives included the evaluation of associations between biomarkers and parameters of volume overload and hemodynamic congestion.
Materials and methodsStudy design and populationThis was a cross-sectional pilot, hypothesis-generating observational study conducted in prevalent patients undergoing chronic HD at Fundació Puigvert. Only patients receiving maintenance HD for at least 6 months were included in order to reduce heterogeneity related to incident dialysis status and early dialysis adaptation.
All evaluations, including clinical assessment, BIS, PoCUS examination, and blood sample collection for biomarker analysis, were performed simultaneously in the pre-dialysis setting during the short interdialytic interval. The unit of analysis was the patient, with a single assessment per subject.
The study was reported according to the STROBE (Strengthening the Reporting of Observational Studies in Epidemiology) guidelines for observational studies.
Inclusion criteriaPatients meeting the following criteria were included:
- 1.
Age ≥18 years receiving HD due to advanced chronic kidney disease according to KDIGO criteria.9
- 2.
Maintenance HD treatment for at least 6 months before inclusion.
- 3.
Provision of written informed consent.
Patients with hemodynamic instability at the time of evaluation, active infection, recent hospitalization, or inability to undergo ultrasound examination or BIS measurement were excluded.
Variables assessedClinical and treatment dataDemographic and clinical variables were collected, including age, sex, hypertension, type 2 diabetes mellitus, heart disease, atrial fibrillation, valvular disease, cerebrovascular disease, chronic lung disease, and cause of kidney disease. Dialysis-related variables included type of vascular access, residual urine output, dialysis vintage, type and duration of HD sessions, usual ultrafiltration volume, and interdialytic weight gain which was recorded at the beginning of the assessment. These variables were collected to characterize the cohort and to explore potential factors influencing cardiovascular remodeling, residual kidney function, ultrafiltration tolerance, and congestion phenotype.
Clinical assessmentA targeted physical examination was performed, including assessment of peripheral edema, dyspnea or orthopnea, pre-dialysis blood pressure, baseline oxygen saturation, and lung auscultation. Patients were categorized according to global clinical assessment into no congestion, mild, moderate, or severe congestion.
Mild congestion was defined by the presence of isolated clinical findings suggestive of fluid overload, including mild peripheral edema or pulmonary crackles in the absence of respiratory symptoms or hypoxemia. Moderate congestion was defined by the coexistence of multiple clinical signs or symptoms of congestion, including edema associated with dyspnea or orthopnea. Severe congestion was defined by overt pulmonary congestion with marked respiratory symptoms, hypoxemia, or severe functional limitation.
BIS assessmentBIS was used to estimate extracellular volume and the degree of overhydration, expressed as absolute overhydration (OH, L) and relative overhydration (OH/ECW, %), using the Body Composition Monitor (BCM®, Fresenius Medical Care). Patients were categorized according to previously validated reference values: normohydration (OH <1.1L or OH/ECW between −6% and +6%), mild volume overload (OH 1.1–2L or OH/ECW 7–15%), moderate volume overload (OH 2.1–3.5L or OH/ECW 15–25%), severe volume overload (OH >3.5L or OH/ECW >25%).
Ultrasound assessment (PoCUS)Ultrasound examinations were performed using a portable device with a convex probe (2–5MHz), following a standardized protocol. All examinations were conducted by a single physician with prior training and experience in PoCUS, including vascular and lung ultrasound.
Lung ultrasound was used to assess B-lines in anterior and lateral lung fields, complemented by posterior lung examination in the sitting position when feasible. The presence of ≥3 B-lines in at least two bilateral lung zones was considered suggestive of pulmonary congestion according to previously described criteria.10,11 Inferior vena cava (IVC) diameter and inspiratory collapsibility were assessed during quiet respiration. An IVC diameter >2cm with inspiratory collapsibility <50% was considered suggestive of elevated right atrial pressure and systemic venous congestion. Portal vein Doppler flow was also evaluated. Mild-to-moderate pulsatility (pulsatility fraction 0.3–0.5) was considered suggestive of early venous congestion, whereas marked pulsatility (>0.5) or discontinuous portal venous flow patterns were considered indicative of more advanced venous congestion.6,7 These parameters were selected as markers of systemic venous congestion due to their feasibility, reproducibility, and increasing use in PoCUS protocols, as well as their ability to reflect right-sided filling pressures.6,7
For descriptive purposes, patients were categorized according to the presence and extent of ultrasound abnormalities, in the absence of a validated reference classification in this population. Mild congestion was defined as isolated pulmonary or systemic venous ultrasound abnormalities, without evidence of combined pulmonary and systemic venous congestion or advanced systemic venous Doppler abnormalities. Moderate congestion was defined by the coexistence of pulmonary congestion and systemic venous abnormalities, including inferior vena cava dilatation and/or mild systemic venous Doppler alterations. Severe congestion was defined as overt pulmonary congestion associated with multiple advanced systemic venous Doppler abnormalities.
Accordingly, for this exploratory analysis, PoCUS-defined congestion was based on the integrated interpretation of pulmonary and systemic venous ultrasound findings suggestive of hemodynamic congestion rather than isolated ultrasound abnormalities.
Echocardiographic data were not systematically included, as the study focused on PoCUS and routinely available bedside tools in the HD unit.
BiomarkersHemoglobin, sodium, albumin, urea, plasma osmolality, N-terminal pro-B-type natriuretic peptide (NT-proBNP), and carbohydrate antigen 125 (CA-125) levels were measured in pre-dialysis blood samples on the same day. Biochemical parameters were collected to characterize the cohort and to explore potential factors influencing fluid distribution, congestion, and biomarker interpretation. NT-proBNP and CA-125 were included as biomarkers related to congestion and myocardial stress and were not used to define or classify volume status. NT-proBNP and CA-125 measurements were performed using electrochemiluminescence immunoassays (ECLIA) on the Roche Diagnostics platform in the hospital central laboratory. Given their role as continuous indicators of underlying pathophysiological processes, no predefined cut-off values were applied, and results were analyzed descriptively and in relation to other parameters.
Primary outcomeThe primary outcome was the exploratory assessment of concordance and discordance between clinical evaluation, BIS-derived extracellular volume parameters, and PoCUS-derived ultrasound findings associated with hemodynamic congestion.
Sample sizeA total of 15 patients were consecutively included. The study was designed as a pilot exploratory analysis.
Ethical considerationsThe study was approved by the Institutional Research Ethics Committee of Fundació Puigvert (reference C2024/49) and was conducted in accordance with the principles of the Declaration of Helsinki. All participants provided written informed consent.
Statistical analysisContinuous variables were expressed as mean±standard deviation or median (interquartile range), depending on distribution. Categorical variables were expressed as frequencies and percentages. Given that BIS, PoCUS, and clinical evaluation assess distinct physiological and hemodynamic domains related to fluid status and congestion, weighted kappa analyses were considered exploratory and descriptive rather than measures of diagnostic equivalence or interchangeability between methods. Spearman correlation analyses were additionally performed to explore relationships between biomarkers and distinct dimensions of extracellular volume overload and hemodynamic congestion. A p-value <0.05 was considered statistically significant.
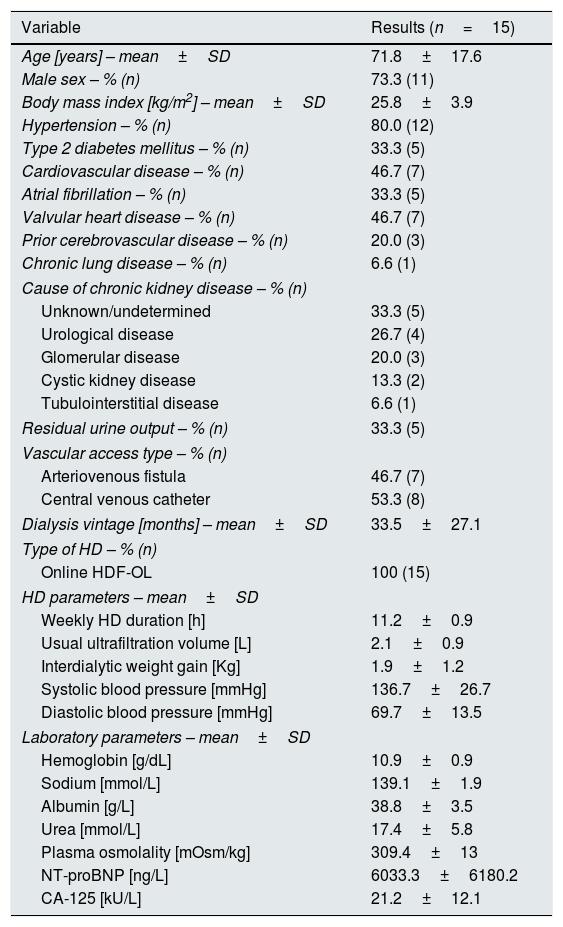
ResultsA total of 15 patients undergoing chronic HD were included, with a mean age of 71.8±17.6 years and a predominance of males (73.3%). The cohort had a high comorbidity burden, including hypertension (80%), cardiovascular disease (46.7%), and type 2 diabetes mellitus (33.3%).
More than half of the patients had a central venous catheter as vascular access, and the mean dialysis vintage was 33.5±27.1 months. All patients were treated with online hemodiafiltration (HDF-OL), with adequate hemodynamic tolerance.
Most patients were anuric; only five (33.3%) had residual urine output greater than 500mL/day.
Baseline clinical and laboratory characteristics are summarized in Table 1.
Baseline characteristics of the study cohort (n=15).
| Variable | Results (n=15) |
|---|---|
| Age [years] – mean±SD | 71.8±17.6 |
| Male sex – % (n) | 73.3 (11) |
| Body mass index [kg/m2] – mean±SD | 25.8±3.9 |
| Hypertension – % (n) | 80.0 (12) |
| Type 2 diabetes mellitus – % (n) | 33.3 (5) |
| Cardiovascular disease – % (n) | 46.7 (7) |
| Atrial fibrillation – % (n) | 33.3 (5) |
| Valvular heart disease – % (n) | 46.7 (7) |
| Prior cerebrovascular disease – % (n) | 20.0 (3) |
| Chronic lung disease – % (n) | 6.6 (1) |
| Cause of chronic kidney disease – % (n) | |
| Unknown/undetermined | 33.3 (5) |
| Urological disease | 26.7 (4) |
| Glomerular disease | 20.0 (3) |
| Cystic kidney disease | 13.3 (2) |
| Tubulointerstitial disease | 6.6 (1) |
| Residual urine output – % (n) | 33.3 (5) |
| Vascular access type – % (n) | |
| Arteriovenous fistula | 46.7 (7) |
| Central venous catheter | 53.3 (8) |
| Dialysis vintage [months] – mean±SD | 33.5±27.1 |
| Type of HD – % (n) | |
| Online HDF-OL | 100 (15) |
| HD parameters – mean±SD | |
| Weekly HD duration [h] | 11.2±0.9 |
| Usual ultrafiltration volume [L] | 2.1±0.9 |
| Interdialytic weight gain [Kg] | 1.9±1.2 |
| Systolic blood pressure [mmHg] | 136.7±26.7 |
| Diastolic blood pressure [mmHg] | 69.7±13.5 |
| Laboratory parameters – mean±SD | |
| Hemoglobin [g/dL] | 10.9±0.9 |
| Sodium [mmol/L] | 139.1±1.9 |
| Albumin [g/L] | 38.8±3.5 |
| Urea [mmol/L] | 17.4±5.8 |
| Plasma osmolality [mOsm/kg] | 309.4±13 |
| NT-proBNP [ng/L] | 6033.3±6180.2 |
| CA-125 [kU/L] | 21.2±12.1 |
SD: standard deviation; HD: hemodialysis; HDF-OL: online hemodiafiltration; NT-proBNP: N-terminal pro-B-type natriuretic peptide; CA-125: cancer antigen 125.
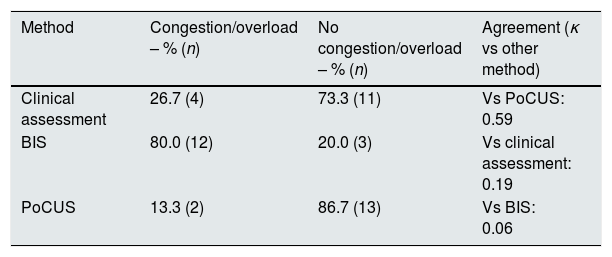
BIS-derived extracellular overhydration was identified in 12 patients (80%), whereas clinical assessment identified signs of congestion in 4 patients (26.7%) and PoCUS in 2 patients (13.3%) (Table 2).
Binary classification of volume overload and congestion across methods.
| Method | Congestion/overload – % (n) | No congestion/overload – % (n) | Agreement (κ vs other method) |
|---|---|---|---|
| Clinical assessment | 26.7 (4) | 73.3 (11) | Vs PoCUS: 0.59 |
| BIS | 80.0 (12) | 20.0 (3) | Vs clinical assessment: 0.19 |
| PoCUS | 13.3 (2) | 86.7 (13) | Vs BIS: 0.06 |
BIS: bioimpedance spectroscopy; PoCUS: point-of-care ultrasonography; κ: Cohen's kappa coefficient.
The most frequent clinical findings suggestive of congestion were peripheral edema in 2 patients (13.3%) and pulmonary crackles in 2 patients (13.3%).
According to BIS classification, 3 patients (20%) were categorized as normohydrated, whereas 5 (33.3%) had mild volume overload, 5 (33.3%) moderate overload, and 2 (13.3%) severe overload.
PoCUS identified mild ultrasound findings suggestive of hemodynamic congestion in 2 patients (13.3%). One patient presented bilateral B-lines without systemic venous ultrasound abnormalities. The second patient showed mild systemic venous congestion characterized by a dilated IVC and mildly pulsatile portal vein Doppler flow without pulmonary ultrasound abnormalities.
Exploratory concordance and discordance between methodsAgreement was moderate between clinical assessment and PoCUS (κ=0.59), whereas it was low between clinical assessment and BIS (κ=0.19) and very low between BIS and PoCUS (κ=0.06) (Table 2).
In the ordinal analysis, BIS classified a greater proportion of patients into moderate and severe categories compared with clinical assessment and PoCUS.
In contrast, PoCUS identified a smaller subset of patients with ultrasound findings suggestive of hemodynamic congestion, with a distribution more closely aligned with clinical assessment.
Detailed distributions across methods are shown in Fig. 1.

Distribution of congestion and volume overload across assessment methods. Simplified binary matrices showing the distribution of patients classified according to clinical assessment, BIS-derived volume overload, and PoCUS-defined congestion. Rows correspond to the first method compared and columns to the second.
BIS: bioimpedance spectroscopy; PoCUS: point-of-care ultrasonography.
NT-proBNP levels showed wide interindividual variability, whereas CA-125 levels exhibited less dispersion.
Patients with clinical signs of congestion had higher NT-proBNP concentrations compared to those without clinical congestion (12,641±7557 vs 3630±3539ng/L; p=0.018).
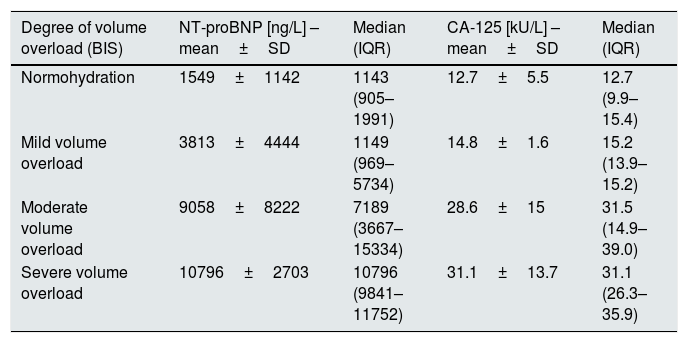
According to BIS classification, NT-proBNP levels increased progressively with higher degrees of estimated volume overload, showing a significant positive correlation (rho≈0.67; p=0.007). Similarly, CA-125 levels showed an increasing trend with greater volume overload, with a significant positive correlation (rho≈0.58; p=0.025) (Table 3).
NT-proBNP and CA-125 concentrations according to BIS-defined volume status categories.
| Degree of volume overload (BIS) | NT-proBNP [ng/L] – mean±SD | Median (IQR) | CA-125 [kU/L] – mean±SD | Median (IQR) |
|---|---|---|---|---|
| Normohydration | 1549±1142 | 1143 (905–1991) | 12.7±5.5 | 12.7 (9.9–15.4) |
| Mild volume overload | 3813±4444 | 1149 (969–5734) | 14.8±1.6 | 15.2 (13.9–15.2) |
| Moderate volume overload | 9058±8222 | 7189 (3667–15334) | 28.6±15 | 31.5 (14.9–39.0) |
| Severe volume overload | 10796±2703 | 10796 (9841–11752) | 31.1±13.7 | 31.1 (26.3–35.9) |
NT-proBNP: N-terminal pro-B-type natriuretic peptide; CA-125: cancer antigen 125; BIS: bioimpedance spectroscopy; PoCUS: point-of-care ultrasonography; IQR: interquartile range.
Patients with ultrasound findings suggestive of hemodynamic congestion had higher NT-proBNP levels compared to those without ultrasound signs of congestion (15,334±11,274 vs 4602±4163ng/L). Ultrasound-detected congestion also showed a moderate positive correlation with NT-proBNP levels (Spearman rho≈0.57; p=0.042).
In contrast, CA-125 levels did not show significant differences according to the presence of ultrasound-detected congestion.
DiscussionThe main finding of this exploratory pilot study is the marked heterogeneity observed among the different tools used to assess extracellular volume overload and hemodynamic congestion in patients undergoing HD. These findings suggest that the different tools capture complementary aspects of fluid status and congestion, rather than simply representing methodological differences between techniques. Therefore, the low agreement observed between methods should not necessarily be interpreted as poor diagnostic performance, but rather as evidence that these techniques evaluate different but potentially complementary pathophysiological constructs.
BIS estimates extracellular volume, whereas PoCUS identifies ultrasound findings associated with elevated filling pressures and venous congestion. Clinical evaluation integrates later and symptom-dependent manifestations, which may explain its closer alignment with ultrasound findings in this cohort.2,4,5
This concept is particularly relevant in HD patients, in whom extracellular volume expansion and hemodynamic congestion may become dissociated. The relationship between volume and congestion is therefore not necessarily linear.6–8 The presence of diastolic dysfunction, which is common in this population, may lead to elevated filling pressures in the absence of overt volume overload, resulting in congestion despite relatively normal volume status. Conversely, increases in extracellular volume may occur without clear clinical or ultrasound manifestations, which may explain the high proportion of patients classified as volume overloaded by BIS compared with PoCUS.
In this context, our findings are consistent with previous studies2,4 showing limited agreement between volume-based techniques and ultrasound tools for assessing congestion, reinforcing the need for a multiparametric approach to fluid status evaluation in HD. PoCUS identified a distinct subset of patients with integrated ultrasound findings suggestive of hemodynamic and systemic venous congestion, which did not necessarily overlap with extracellular volume expansion detected by BIS.10,11
Regarding biomarkers, NT-proBNP levels were associated with both clinical congestion and BIS-estimated volume overload, suggesting that this marker primarily reflects increased filling pressures and myocardial stress3,12 rather than volume per se. In contrast, CA-125 showed an increasing trend with greater volume overload, consistent with its role as a marker of chronic tissue congestion,13,14 although its utility in detecting acute changes in HD patients appears to be limited.
It should be noted that the low proportion of patients with ultrasound-detected congestion in our cohort, all of mild severity, may have influenced the magnitude of the observed discordance and limits the ability to establish more robust comparisons between methods.
From a clinical perspective, these findings have relevant implications. The use of tools that exclusively assess volume may lead to an overestimation of fluid overload, whereas the integration of techniques targeting hemodynamic congestion, such as PoCUS, may allow a more individualized approach to ultrafiltration adjustment,1,15 particularly in patients with cardiovascular comorbidity. In this sense, combining parameters of volume and congestion may contribute to more precise decision-making, enabling more conservative or progressive ultrafiltration strategies according to the individual patient profile.
This study has several limitations. First, the absence of echocardiographic data precludes a comprehensive characterization of cardiac function and limits the ability to fully explore congestion phenotypes. However, this study was designed as a pilot study focusing on readily available bedside tools in routine HD practice, where access to echocardiography is often limited. Future studies incorporating larger cohorts, comprehensive cardiac phenotyping, and standardized congestion assessment are required to validate these exploratory findings and better define congestion phenotypes and their clinical implications.
Second, the small sample size and exploratory, hypothesis-generating pilot design limit the generalizability of the findings and preclude definitive conclusions regarding congestion phenotypes or method performance. Third, the lack of standardization using validated clinical congestion scores and the absence of blinding between evaluators may have introduced bias. Finally, no adjustment was made for potential confounders, such as cardiac function, dialysis vintage or the presence of atrial fibrillation, which may influence the interpretation of biomarkers and ultrasound findings. In addition, no formal intraobserver or interobserver reproducibility assessment was performed for ultrasound parameters due to the pilot nature of the study.
Overall, our findings suggest that fluid status assessment in HD patients requires the integration of tools exploring different and potentially complementary pathophysiological aspects.
ConclusionsDifferent bedside tools identified divergent patterns of extracellular volume overload and hemodynamic congestion in HD patients. BIS, PoCUS and clinical assessment should not be interpreted as equivalent or interchangeable tools, but rather as complementary methods providing distinct physiological and hemodynamic information relevant to fluid status evaluation. Biomarkers provided additional information regarding different volume overload and congestion profiles, although these findings should be considered exploratory.
These findings support the use of a multiparametric approach to fluid status assessment and treatment individualization. The observed discordance between methods likely reflects the multidimensional nature of congestion in HD patients, including the dissociation between extracellular volume expansion and hemodynamic/systemic venous congestion, rather than simple methodological disagreement. Given the pilot and hypothesis-generating nature of this study, larger investigations incorporating comprehensive cardiac phenotyping and standardized congestion assessment are needed to confirm these findings.
FundingThis research did not receive any specific grant from funding agencies in the public, commercial, or not-for-profit sectors.
Conflicts of interestThe authors declare no conflicts of interest related to this work.




