



Of the patients receiving dialysis in a large Canadian renal program, 60.7% reported regretting their decision to start dialysis.1 When asked why dialysis had been chosen over conservative care, 51.9% attributed the decision primarily to their physician's wish and 13.9% to their family's wish, rather than their own.1 At the same time, fewer than one in ten patients (9.9%) reported having discussed end-of-life care preferences with their nephrologist in the previous 12 months, and most had limited awareness of supportive care options, with 83.4% not knowing what palliative care is and 71.8% not knowing what hospice is.1
These figures do not simply reflect communication gaps. They point to a deeper problem: many patients embark on dialysis without fully understanding that it is a choice, and that this choice can be revisited, limited, or reframed over time. These observations raise broader questions about how dialysis decisions are made and contextualized within the growing burden of chronic kidney disease (CKD). CKD represents a major global public health challenge, affecting nearly 10% of the adult population worldwide. As the disease progresses, an increasing number of patients require kidney replacement therapy (KRT), exposing millions of individuals to complex, high-burden treatment decisions.2,3 In Spain, the population receiving KRT is predominantly older, with a growing proportion of patients aged 75 years or older. This demographic shift is associated with a substantial mortality burden and complex clinical trajectories characterized by multimorbidity, frailty, and functional decline. Overall annual mortality among patients receiving KRT is approximately 7.7%, with marked differences by modality (13.4% in HD, 9.1% in PD, and 2.9% among transplant recipients). Among HD patients aged 75 years or older, annual mortality approaches 18%.4
In this context, quality of life (QoL) has become a central outcome of care, particularly in older and frail patients. Evidence from the Geriatric assessment in OLder patients starting Dialysis (GOLD)study highlights the trade-offs associated with dialysis initiation in older adults. Baseline QoL was similar between patients starting dialysis and those managed conservatively. Over six months, QoL remained stable in the dialysis group, whereas a small but clinically relevant decline was observed in conservatively managed patients, at the cost of a substantially higher hospitalization rate among those receiving dialysis. Among patients aged 80 years or older, dialysis did not confer a survival benefit.5
Despite this high symptom burden, progressive functional decline, and substantial risk of death, advance care planning (ACP) remains limited in routine nephrology practice. Fewer than 30–40% of patients receiving dialysis report having engaged in structured discussions regarding prognosis, goals of care, or future scenarios. When advance directives exist, they rarely address dialysis-specific decisions such as treatment limitation or withdrawal.6 This gap has relevant clinical consequences. These decisions are frequent but often made late, during acute decompensations, and without a prior deliberative process that integrates prognosis and patient values.6
The need for shared decision-making in dialysis: beyond a binary choiceThese observations highlight the limitations of framing dialysis decisions as a binary choice. In advanced CKD, decision-making should instead be understood as a shared, structured, multidisciplinary, and dynamic process, centered on patient values rather than isolated interventions.7,8 This represents a fundamental shift from decision-making centered on treatments to decision-making centered on patients.
This shift is further supported by supportive care frameworks and KDIGO recommendations, which emphasize iterative discussions integrating prognosis, goals of care, and evolving clinical contexts.9,10 Within this context, the concept of adequation of therapeutic effort provides a practical framework to operationalize shared decision-making (SDM).8,11 SDM supports an adequation of therapeutic effort that patients and their families can understand and accept, based on a clear understanding of the patient's clinical situation. Rather than focusing on isolated interventions, this approach emphasizes jointly defining proportional goals of care aligned with prognosis, functional status, and patient values based on a multidisciplinary approach.8,12 While territorial frameworks in other areas of chronic care emphasize predefined levels of therapeutic intervention rather than crisis-driven decisions, comparable structured approaches remain largely absent in nephrology, contributing to variability in practice and reinforcing the need for dialysis-specific models aligned with SDM.7,13 These frameworks conceptualize therapeutic intensity as a dynamic construct that can be adapted over time, ranging from life-sustaining to comfort-focused care. Applied to dialysis, this approach allows initiation, continuation, adaptation, or withdrawal of treatment to be explicitly aligned with prognosis, functional status, reversibility of complications, and, critically, patient values. Establishing levels of therapeutic intervention provides a common language for patients, families, and professionals, facilitates continuity across care settings, and helps avoid disproportionate or non-beneficial interventions. Recent evidence reinforces the need to reconsider how dialysis decisions are made in patients with advanced CKD, particularly among older and frail individuals.14,15 In routine clinical practice, dialysis initiation often remains the default pathway despite limited life expectancy, high comorbidity, or functional impairment, overlooking the heterogeneity of clinical trajectories and the impact of dialysis on daily life, symptom burden, and functional independence.16 Many patients report that dialysis discussions focus primarily on technical aspects and survival, with limited attention to individual goals and values, resulting in initiation or continuation of treatment without a clear understanding of its impact on QoL, autonomy, or the balance between benefit and burden.17 This mismatch is particularly evident in situations of prognostic uncertainty, where the expected survival benefit of dialysis is modest, yet treatment burden remains high. A more appropriate approach acknowledges that decision-making in advanced CKD is dynamic and evolves over time, considering the advanced illness progression and person-centred palliative care needs at the end of life.18 Rather than framing dialysis as a single, irreversible choice, care should allow for graduated levels of intervention, time-limited therapeutic trials, and explicit multidimensional reassessment of health status and needs following intercurrent events.12
A framework for levels of therapeutic intervention in dialysis: the LTI-Dialysis frameworkThe LTI-Dialysis (level of therapeutic intervention in KRT) framework applies the principles of therapeutic proportionality and SDM to dialysis care, allowing the intensity, goals, and limits of KRT to be defined (Fig. 1). In doing so, it moves beyond the binary question of dialysis yes or no, providing a structured way to define therapeutic goals and limits in line with approaches established in other advanced illness trajectories.7 In other advanced illness trajectories, particularly oncology, structured approaches already align treatment intensity with prognosis and goals of care. In our region, this concept has been extended to multimorbid non-oncological patients through territorial protocols of therapeutic intensity adequation,13 supported by tools such as NECPAL, which facilitate the early identification of patients with advanced chronic conditions and palliative care needs.19–22 Within this context, the diagnostic and therapeutic assignment model (MADiT) was introduced as a practical tool to support clinical decision-making once a level of therapeutic intervention has been defined, providing operational guidance when uncertainty arises regarding how intensively to act within an agreed level of care.23 Despite the availability of such approaches in other fields, nephrology has largely lacked a dialysis-specific framework to define levels of therapeutic intervention. Building on evidence from person-centred care and SDM in kidney disease.8,11,16,24,25

The LTI-Dialysis framework: levels of therapeutic intervention in kidney replacement therapy. LTI-Dialysis framework illustrating four levels of therapeutic intervention in kidney replacement therapy (KRT): full dialysis for survival (LTI-D 1), full dialysis with explicit limits (LTI-D 2), adapted or palliative dialysis with three sublevels (LTI-D 3A–3C), and withdrawal of dialysis with conservative management (LTI-D 4). The lower panel depicts practical applications shown in the figure, including proportional supportive therapies, alignment of treatment intensity with patient goals and clinical trajectory, and guided transitions from peritoneal dialysis (PD) to hemodialysis (HD). Abbreviations: LTI, level of therapeutic intervention; HD, hemodialysis; PD, peritoneal dialysis; ICU, intensive care unit; CPR, cardiopulmonary resuscitation.
We propose the LTI-Dialysis framework as a dialysis-specific adaptation designed to define therapeutic goals and limits, while allowing proportional clinical action within each level.
LTI-D 1: full dialysis oriented to survivalLTI-D 1 represents the highest level of therapeutic intervention. Dialysis is delivered with maximum therapeutic intensity and a clear survival-oriented goal. Treatment follows clinical guidelines, targets full biochemical control, and includes optimal vascular access. There are no limits to hospitalization, intensive care unit (ICU) admission, cardiopulmonary resuscitation (CPR), invasive mechanical ventilation, or other life-sustaining therapies. Patients at this level are typically candidates for kidney transplantation or other advanced therapies.
LTI-D 2: full dialysis with explicit therapeutic limitsLTI-D 2 corresponds to active, life-prolonging dialysis delivered within clearly predefined limits of escalation. However, specific interventions such as CPR, endotracheal intubation, invasive mechanical ventilation, or ICU admission are excluded based on prior SDM. Importantly, LTI-D 2 allows proportional supportive therapies despite limits to escalation. Selected interventions, such as non-invasive ventilation, vasoactive drugs, transfusions, or short-term dialysis adjustments, may still be appropriate when consistent with goals of care. Hospitalization is selective, dialysis prescriptions may be adapted to improve tolerance, and periodic reassessment of clinical benefit is essential.
LTI-D 3: adapted or palliative dialysisLTI-D 3 encompasses situations in which dialysis is primarily oriented toward symptom control and QoL rather than survival. This level includes three clinically distinct sublevels reflecting progressive therapeutic de-escalation:
LTI-D 3A: conditional dialysis. Dialysis is continued as a time-limited or conditional intervention, often following an intercurrent event. Measures typically associated with LTI-D 2 may be temporarily implemented, with explicit, pre-agreed criteria for withdrawal if the expected benefit is not achieved. This sublevel is particularly useful when prognosis is uncertain and a therapeutic trial is ethically justified.
LTI-D 3B: palliative dialysis. Dialysis is delivered with reduced intensity and strictly symptom-driven goals. At this stage, disease-directed interventions are generally avoided, and treatments such as antibiotics or transfusions are considered only when their primary intent is symptom relief rather than disease modification or life prolongation. When such interventions are initiated, their continuation should be contingent on meaningful symptomatic benefit; in the absence of improvement, care should progress toward a more comfort-focused LTI. Treatment decisions prioritize comfort, symptom control, and minimization of treatment burden.
LTI-D 3C: transitional dialysis. LTI-D 3C represents a transitional bridge toward dialysis withdrawal. Dialysis may be temporarily maintained to facilitate symptom control, family preparation, or organizational planning. However, this is done without introducing or maintaining active disease-directed treatments. The focus progressively shifts toward end-of-life care, with early integration of palliative care teams.
Importantly, transitions between LTI-D levels should not be interpreted as a linear progression toward dialysis withdrawal. Rather, the framework is dynamic and allows movement in both directions according to the patient's clinical trajectory. While clinical deterioration may lead to de-escalation of therapeutic intensity, some patients may experience stabilization or improvement that justifies reconsidering previously limited interventions. This trajectory-based approach ensures that dialysis decisions remain centered on the patient's evolving condition, priorities, and goals of care rather than on the disease alone.
LTI-D 4: withdrawal of dialysis and conservative managementLTI-D 4 corresponds to the lowest level of therapeutic intervention. Dialysis is suspended, and care focuses exclusively on comfort, symptom control, and psychosocial, spiritual, and family support. Management may take place at home, in hospital, or in specialized palliative care settings. When indicated and consistent with patient wishes, palliative sedation may be used. Death is generally expected within days to weeks.
Application of LTI-Dialysis to transitions from peritoneal dialysis to in-center hemodialysisIn patients treated with PD, the LTI-Dialysis framework is particularly useful when considering transition to in-center HD. Technique failure, peritonitis, or acute clinical deterioration often prompt implicit escalation to HD. Applying LTI-Dialysis reframes this decision as a goal-oriented and proportional choice, explicitly aligned with the patient's level of therapeutic intervention. Transitions from PD to HD are generally appropriate in LTI-D 1 and LTI-D 2. They may be selectively considered in LTI-D 3A as part of a conditional trial. In contrast, such transitions are usually inconsistent with goals of care in LTI-D 3B, LTI-D 3C, or LTI-D 4.
A clinical scenario further illustrates how LTI-Dialysis levels may evolve along a patient's trajectory.
A patient receiving maintenance HD with multiple comorbidities was initially managed under LTI-D 1, with no limitations to ICU support. The patient was later admitted with a catheter-related bloodstream infection complicated by infective endocarditis and required prolonged ICU care, initially receiving continuous kidney replacement therapy (CKRT). After stabilization and transition back to intermittent HD, the patient remained profoundly frail with severe cardiac dysfunction and recurrent intradialytic hypotension, and the clinical course continued to deteriorate despite transfer to a rehabilitation facility. Following shared decision-making with the patient and family, the level of therapeutic intervention was revised toward a symptom-centered approach consistent with LTI-D 3 palliative dialysis. This example illustrates how dialysis intensity and therapeutic goals may be reassessed as the patient's clinical trajectory evolves.
ACP and implementation of LTI-DialysisThe clinical usefulness of the LTI-Dialysis framework ultimately depends on its implementation in routine care. Crucially, defining the LTI-Dialysis level must be grounded in patients’ values, preferences, beliefs, and life priorities.7
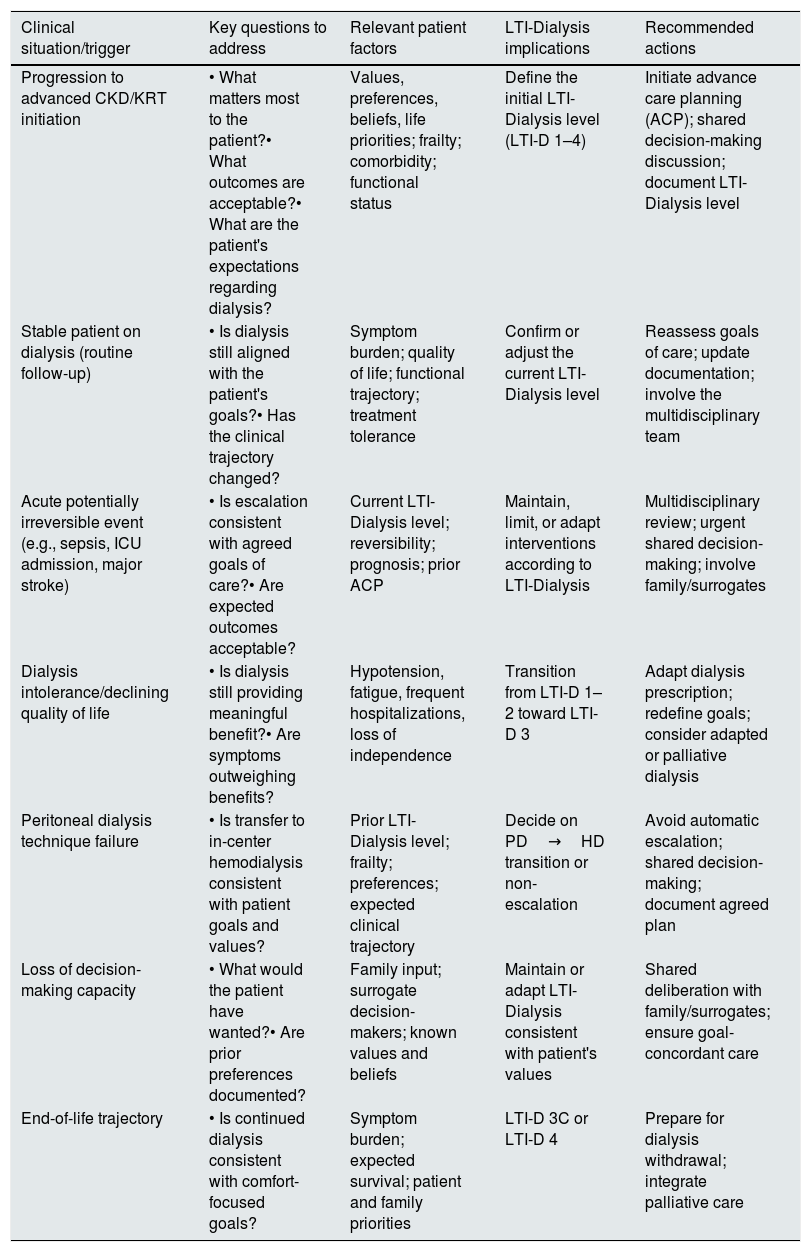
Implementation of the LTI-Dialysis framework requires a structured and multidisciplinary approach. In routine practice, definition of the LTI-D level should emerge from shared decision-making involving the nephrology team, dialysis nurses, geriatricians when available, the patient, and family members, with integration of palliative care specialists when appropriate (Table 1). Dialysis nurses play a particularly important role, as they are often the first to identify changes in functional status, treatment tolerance, symptom burden, or patient priorities during routine dialysis care. Rather than representing a one-time decision, the assigned level of therapeutic intervention should be documented within the advance care planning process and revisited over time. Reassessment is particularly important after major clinical events such as hospitalizations, functional decline, dialysis intolerance, or modality failure. In this way, LTI-Dialysis becomes a dynamic tool that supports proportional adjustments in treatment intensity while maintaining alignment with patient values and goals of care.
Practical implementation of LTI-Dialysis in routine clinical care.
| Clinical situation/trigger | Key questions to address | Relevant patient factors | LTI-Dialysis implications | Recommended actions |
|---|---|---|---|---|
| Progression to advanced CKD/KRT initiation | • What matters most to the patient?• What outcomes are acceptable?• What are the patient's expectations regarding dialysis? | Values, preferences, beliefs, life priorities; frailty; comorbidity; functional status | Define the initial LTI-Dialysis level (LTI-D 1–4) | Initiate advance care planning (ACP); shared decision-making discussion; document LTI-Dialysis level |
| Stable patient on dialysis (routine follow-up) | • Is dialysis still aligned with the patient's goals?• Has the clinical trajectory changed? | Symptom burden; quality of life; functional trajectory; treatment tolerance | Confirm or adjust the current LTI-Dialysis level | Reassess goals of care; update documentation; involve the multidisciplinary team |
| Acute potentially irreversible event (e.g., sepsis, ICU admission, major stroke) | • Is escalation consistent with agreed goals of care?• Are expected outcomes acceptable? | Current LTI-Dialysis level; reversibility; prognosis; prior ACP | Maintain, limit, or adapt interventions according to LTI-Dialysis | Multidisciplinary review; urgent shared decision-making; involve family/surrogates |
| Dialysis intolerance/declining quality of life | • Is dialysis still providing meaningful benefit?• Are symptoms outweighing benefits? | Hypotension, fatigue, frequent hospitalizations, loss of independence | Transition from LTI-D 1–2 toward LTI-D 3 | Adapt dialysis prescription; redefine goals; consider adapted or palliative dialysis |
| Peritoneal dialysis technique failure | • Is transfer to in-center hemodialysis consistent with patient goals and values? | Prior LTI-Dialysis level; frailty; preferences; expected clinical trajectory | Decide on PD→HD transition or non-escalation | Avoid automatic escalation; shared decision-making; document agreed plan |
| Loss of decision-making capacity | • What would the patient have wanted?• Are prior preferences documented? | Family input; surrogate decision-makers; known values and beliefs | Maintain or adapt LTI-Dialysis consistent with patient's values | Shared deliberation with family/surrogates; ensure goal-concordant care |
| End-of-life trajectory | • Is continued dialysis consistent with comfort-focused goals? | Symptom burden; expected survival; patient and family priorities | LTI-D 3C or LTI-D 4 | Prepare for dialysis withdrawal; integrate palliative care |
Abbreviations: ACP, advance care planning; CKD, chronic kidney disease; HD, hemodialysis; ICU, intensive care unit; KRT, kidney replacement therapy; LTI-Dialysis, level of therapeutic intervention in kidney replacement therapy; PD, peritoneal dialysis; QoL, quality of life; SDM, shared decision-making.
When patients lack decision-making capacity or do not have advance directives, family members and legally designated surrogates play a central role in reconstructing these values and guiding decisions. Periodic reassessment is essential, particularly following hospitalizations, functional decline, dialysis intolerance, modality failure, or acute potentially irreversible events. By converting patient values into actionable clinical guidance, LTI-Dialysis helps reduce decisional regret and align care with patient priorities.24,26 Without such structured approaches, SDM risks remaining an aspirational concept rather than a reproducible clinical practice.
ConclusionIn advanced CKD, moving beyond a binary approach to dialysis decision-making is essential, and the LTI-Dialysis framework offers a structured and patient-centered way to align dialysis intensity with clinical trajectories and patient values.




